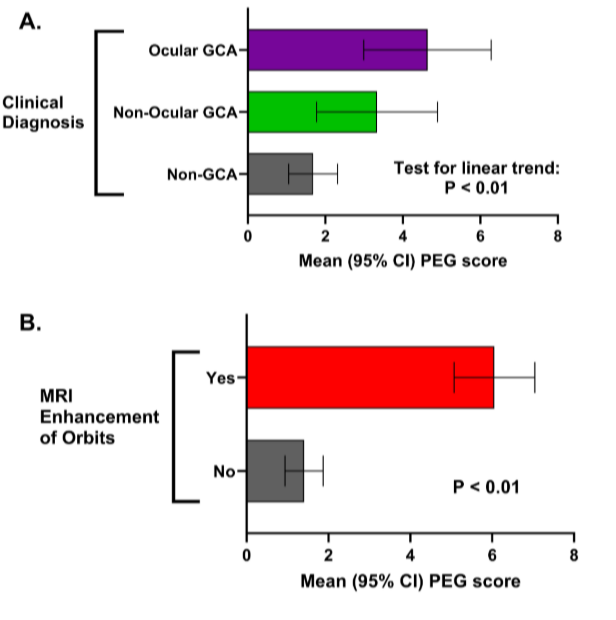
The treatment paradigm for Giant Cell Arteritis (GCA) has been a binary approach to the presence or absence of vasculitis. When GCA is present, we institute high doses of glucocorticoids for treatment of the inflammatory process. This approach is not well individualized to the patient as we do not account for the degree of inflammation that may or may not be present in the disease. Improved markers to stratify the extent of inflammation can help to tailor a more personalized approach to treatment.

All News
Article
Article
This has been an interesting ACR meeting in terms of PMR updates. I would argue that we are still far too wedded to glucocorticoids only in the management of PMR. Yes, some patients will do fine with just glucocorticoids but we persist far too long with a glucocorticoid only strategy in others who clearly need an alternative as glucocorticoid adverse events multiply.
#ACR24: What I learned in Sjogren's, Takayasu's and CAR-T
Dr. Janet Pope reviews abstract 2527 and abstract 1696.
https://t.co/rrrGnOhfIV https://t.co/Ht1UTtYOLI
SELECTing the right patients: upadacitinib in GCA
Dr. Brian Jaros reports on abstract 1695, presented at #ACR24.
https://t.co/x8lLTviOKk https://t.co/yXwwrdgIyu
🌟IgG4RD: Lessons from the first 20 years🌟by Prof John Stone
⭐️Lesson 1- IgG4RD is a variable vessel vasculitis
✨Can cause small vessel vasculitis of the skin
✨One of few vasculitis causing coronary arteritis in adults
⭐️Lesson 2- IgG4RD is more common and severe in males… https://t.co/PvFXyOl5bp https://t.co/hAMelBoZvB
A new score to quantify GCA inflammation?
The treatment paradigm for Giant Cell Arteritis (GCA) has been a binary approach to the presence or absence of vasculitis. When GCA is present, we institute high doses of glucocorticoids for treatment of the inflammatory process. #ACR24… https://t.co/b5H7KOtZPC https://t.co/AvrwHcXI7r
JAK inhibitors in GCA?
We have a phase 3 trial in giant cell arteritis back on the opening day plenary stage. The SELECT-GCA study, looking at upadacitinib in GCA, was scheduled to anchor the #ACR24 opening plenary for a reason - it is highly notable and badly needed.… https://t.co/aJ3uao1wD7 https://t.co/6ao2OoODHg
ANCA Vasculitis "Eye": Can rituximab help?
Dr. Janet Pope discusses abstract 0726 at #ACR24
https://t.co/KzYcmjon8D https://t.co/KDIi1vJE4P
Brian Jaros, MD
Tweet
Hypoxia seems to exacerbate neutrophil activation by ANCA
- enhanced F-Actin polymerization
- enhanced NET formation
Could hypoxia predilection in certain tissues (kidney, lung) lead to the AAV phenotypic disease patterns?
@RheumNow #ACR24 https://t.co/KxaeMvkd2t
Brian Jaros, MD
Tweet
Hydralazine - known culprit of drug-induced AAV
How does hydral (H) AAV differ from primary (1) AAV?
💥 High dual positivity MPO/PR3
💥 DAH / pleuritis more common in H-AAV
💥 ENT, constitutional, nervous, ILD in 1-AAV
💥 More 6mo remission in H-AAV
@rheumnow #ACR24 Abst 2496
SELECT-GCA suggests JAKis may be the new kid on the block
Clinicians treating giant cell arteritis (GCA) have long had to contend with a disappointingly limited selection of drugs from which to select.
https://t.co/vtJzwFZMBq https://t.co/dikMRwjIZY
Brian Jaros, MD
Tweet
Risk stratification of GCA pts: who might lose vision?
Cranial MRI with vessel wall enhancement used to calculate additive score... # of vessels affected
Higher scores a/w ocular GCA > non-ocular GCA > no GCA and decreased w/ tx
@RheumNow #ACRbest #ACR24 https://t.co/knDVrl84Qs
Continuing or Stopping Low Dose Glucocorticoids in GPA
Dr. Mike Putman reports about plenary session abstract 0774 (the TAPIR study) about how and when patients can stop steroids in GPA. #ACR24
https://t.co/OWqN0jmkc1 https://t.co/foOaVRtGiV
Richard Conway
Tweet
Yang et al. Cranial vessel wall MRI in GCA. Quantitated with PEG score. PEG score ocular GCA>non-ocular GCA>non-GCA. Decreases with treatment. @RheumNow #ACR24 Abstr#2650 https://t.co/e26urOpb7V https://t.co/eekQbzmKYm
Eric Dein
Tweet
A#2651
Vasculitis w VEXAS
81 men, median age 67 - 27% had evid of vasculitis, variable size vessel
22% SVV- 17/18 cutaneous, one peritubular capillaritis on renal bx
2.5% MVV (2 cutan), LVV (2 carotid thickening, 1 had +TA bx), ANCA+
@RheumNow #ACR24 https://t.co/puablIBLCP
Richard Conway
Tweet
Sullivan et al. Vasculitis in VEXAS. 81 patients. 27% vasculitis. Cutaneous SVV 20%, AAV 2.5%, cutaneous MVV 2.5%, LVV 2.5%. @RheumNow #ACR24 Abstr#2651 https://t.co/AV3RcuSKpV https://t.co/xrax025TzP
Eric Dein
Tweet
A#2648
PET for GCA
Delayed imaging at 180 min improve dx performance for pts on GCs
Optimal PET w/in 3 days of GC, most patients unable to do w/in that window
Delay has sensitivity 92% even on prednisone - may be good tool for pts unable to get early PET/CT
#ACR24 @RheumNow https://t.co/kxpNfRqkGN
Eric Dein
Tweet
A#2650
MRI can show extent of vessel wall inflamm to guide severity of GCA
Brain & orbital MRI performed
Assessed 7 arteries bilaterally -> CAMRIS-GCA MRI score (0-10)
33 GCA (17 ocular), 41 not GCA
CAMRIS-GCA ass w/ ocular GCA, higher severity. Improved w Rx
@RheumNow #ACR24 https://t.co/19XCuZJXqF
Disseminated acanthamoeba : pt with modular painful skin lesions on his palms and scalp— initially dx’d with a cutaneous vasculitis- he got worse with immunosuppression. Imaging and histology shown #ThievesMarket #ACR24 @RheumNow https://t.co/FjJ0Sk0Kxt
sheila
Tweet
A systematic review & meta-analysis by Dr. JBCorrea et al show that the ff immune-mediated dses are assocd w/⬆️ ocurrence risk after covid19 infection 👇
Behcets
SpA
SS
SLE
PMR
Pso
RA
Sjogrens
T1DM
Vasculitis
IBD
Ask prior covid infexn in pts history
@RheumNow #ACR24 abs2614 https://t.co/TIEglPrmvL