Anti-Rheumatic Rx

Dr. John Cush
@RheumNow
EGPA Treatment: A new Era with the E-MERGE trial? EGPA is the rarest of the ANCA-associated vasculitides. Compared with GPA and MPA, EGPA has a mechanistically distinct pathophysiology involving eosinophil-mediated inflammation. This distinct mechanism has driven the https://t.co/gP5y6rCUJH
Janet Pope
@Janetbirdope
#GCA #Flares in year 2 Of #upadacitinib in remission at end of yr 1 Randomized to UPA-UPA Vs UPA-PBO No surprise, on Yr2 PBO ⬆️flares ⬆️pred ⬆️CRP & ESR if flare but higher in no Rx group Take home Rx likely needed for 2 yrs in #GCA #ACR26 @RheumNow @ACRheum #abst1892
Dr. John Cush
@RheumNow
The Weight of Evidence Every rheumatologist knows this patient. Her ASDAS is 3.4. Her CRP is normal, her MRI is quiet, and she is on her third biologic. The reflex is to reach for a fourth. Abstracts from #ACR26 make a quietly radical case against this reflex. https://t.co/skjZIJuq1u
Brian Jaros, MD
@Dr_Brian_MD
Who stays on PsA Therapy? British prospective PsA registry: 815 pt on b/tDMARD Factors affecting drug d/c: - PDE-4 use - higher BMI - enthesitis - lower physician global assessment - polysymptomatic stress Protective: - concomittent csDMARD use #Abst1324 @RheumNow #ACR26
Eric Dein
@ericdeinmd
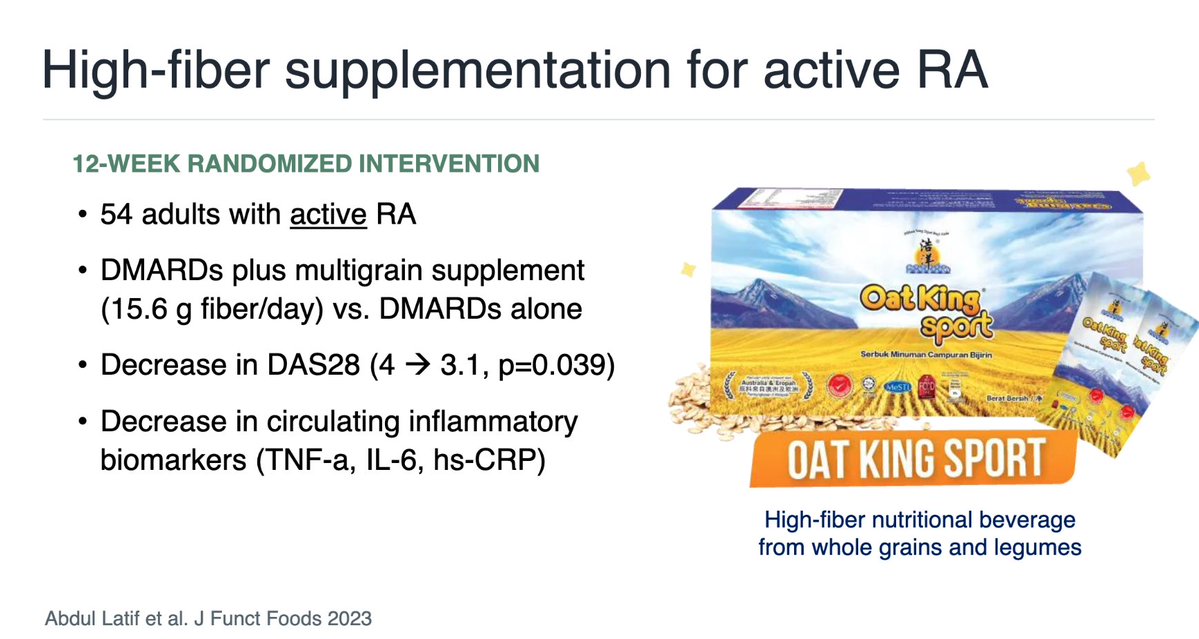
Fiber prebiotic for RA? #ACR26 @RheumNow 1 month high fiber intervention reduces pro-inflammatory cytokines 54 pts active RA given fiber supplement. Decrease DAS28 4->3.1, p=0.04 RCT of inulin - impr DAS28 (p=.02), TJC, SJC, CRP. Not in VAS pain/ESR https://t.co/rWvVdGy0EP
Mrinalini Dey
@DrMiniDey
Why do MTX metabolite profiles vary? PROMOTE/JIA linked FPGS variants to lower long-chain:short-chain MTX-polyglutamate ratios in a genetic analysis of 140 children. Supports precision medicine strategies aimed at identifying non-responders early in JIA #1824 #ACR26 @Rheumnow
×