Clinicians often come across the scenario of a patient with well-controlled spondyloarthritis where the ASDAS in the low disease activity range, CRP normalised, joints clinically quiet. However, the patient returns to the clinic still reporting significant pain. Their rheumatologist adjusts the biological, waits, returns. The pain persists.

All News
Article
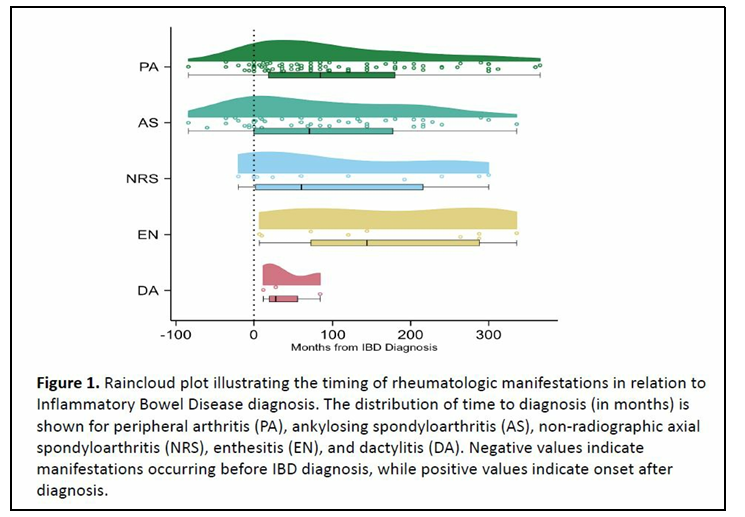
RD in #IBD: 18.6% of 650 IBD pts affected, most commonly peripheral arthritis and AxSpa. Key finding: 14% of rheumatic manifestations preceded IBD diagnosis. Rheumatologists may see these pts first. GI-rheum collaboration is essential. @RheumNow #EULAR2026 POS0807 https://t.co/028yzOxJ2R
Antoni Chan MD (Prof)
Tweet
Over 10 years in the GESPIC cohort, males with #axSpA had lower ASDAS/BASDAI and enthesitis but double the odds of significant spinal radiographic progression vs females (OR 2.08). Symptoms don’t always correlate to structural damage Abstr OP0101 @RheumNow #EULAR2026
After TNFi secondary failure: does MOA switch beat TNFi cycling? UK RWD (n=155): yes for #PsA (76% vs 57% drug survival at 12m) and axSpA (80% vs 68%), but not RA. Yet 74% of axSpA pts still got another TNFi. Evidence vs practice gap in plain sight. @RheumNow #EULAR2026 POS0776
Real-world bimekizumab in SpA/#PsA (BIMPACT, n=223): 76% retention at 12mo, even with 54% having prior IL-17i exposure. Effective after IL-17Ai failure. Oral candidiasis higher in PsA (16.5%) vs SpA (3.3%); led to discontinuation in ~25%. @RheumNow #EULAR2026 POS0798/POS0810
sheila
Tweet
What defines MRI indicative of axSpA?
This systematic lit review show adapting more stringent cutoffs in BME (>=4 SIJ quads, erosion >=3 quads, fat >=5 SIJ quads) & combined BME + structural lesions inc specificity.
Time for updated definitions?
AbsPOS0866 @RheumNow #EULAR2026 https://t.co/gkVbcOAiD3
#OP0241 FASTLANE phase 4 trial showed TOFA was superior to PBO in early active axSpA, achieving significantly higher ASDAS inactive disease rates at 16 weeks (26.4% vs 7.4%) on background of naproxen. MRI osteitis improvement numerically favoured TOFA. #EULAR2026 @RheumNow https://t.co/dGETjkmfrh
sheila
Tweet
Impt pts to consider in D2T CLE by Prof Wittmann:
If tx is not working, ask yourself: is the dx correct? adherence?
Main message: treat early
When damage is present, tx doesn’t really provide considerable improvements
Future drxns? Endotype-directed tx
@Rheumnow #EULAR2026 https://t.co/hB48aD7jx5
#OP0240 phase 3 data showed that the pan-JAK inhibitor gecacitinib significantly improved disease activity, function, MRI inflammation and quality of life in active radiographic axSpA versus placebo at 16 weeks, with ASAS40 responses of 51.9% vs 12.9%. #EULAR2026 @RheumNow https://t.co/6oojvvFmk0
#OP0239: validating 2025 ASAS-SPARTAN axSpA classification criteria in the SPACE cohort. Revised criteria showed high specificity but lower sensitivity than 2009 criteria, reflecting greater emphasis on imaging & less reliance on clinical features alone. #EULAR2026 @RheumNow
#OP0238: French SNDS cohort found longer exposure to targeted therapies in SpA (>6months) was assoc with a lower overall cancer risk vs shorter exposure, esp for haematologic malignancies. Data add to long-term safety evidence for targeted therapies in SpA. #EULAR2026 @RheumNow
#OP0237 reports positive phase 3 data for the selective JAK1 inhibitor ivarmacitinib in active nr-axSpA. ASAS40 responses at Week 12 significantly higher vs placebo (39.7% vs 24.8%), with sustained efficacy through Week 24 and no new safety signals observed. #EULAR2026 @RheumNow https://t.co/JZLQ0Ywlio
After failure of a first TNFi in axSpA, #OP0235 from ROC-SpA trial found no superiority of switching to an IL-17A inhibitor over cycling to second TNFi. ASAS40 responses at Week 24 similar with both strategies, supporting individualised treatment decisions. #EULAR2026 @RheumNow
Catching up with the “Optimising care in SpA” at #EULAR2026 #OP0234 Phase 3 OLINGUITO trial showed filgotinib significantly improved ASAS40 responses vs PBO in both radiographic and non-radiographic axSpA by Week 16, with responses maintained through Week 52. @RheumNow #EULARBest https://t.co/axn6Zv52RA
sheila
Tweet
FASTLANE study Ph4 RCT on TOFA+NPX vs. PBO+NPX for early active axSpA TOFA arm significantly achieved inactive dse vs. PBO (p=0.006) at wk 16. Similar results seen in secondary efficacy endpts. Interesting results supporting TOFA use AbsOP0241 @RheumNow #EULAR2026 #EULARBest https://t.co/PQYzE1zm0h
Antoni Chan MD (Prof)
Tweet
Mean disease duration in the tofacitinib arm was just 0.57 years since diagnosis. This is genuinely early #axSpA and JAK1 inhibition achieves near-remission rates above placebo. An oral option for early axSpA Abstr#0241 @RheumNow #EUlAR2026
Antoni Chan MD (Prof)
Tweet
Tofacitinib achieved ASDAS inactive disease in 26.4% of patients with early #axSpA (back pain ≤2 years) vs 7.4% placebo at 16 weeks (p=0.006). First RCT of advanced therapy in very early axSpA Abstr#0241 @RheumNow #EULAR2026
Antoni Chan MD (Prof)
Tweet
Day 2 of #EULAR2026 Studies to look forward today in #axSpA: new classification criteria performance, sex differences in disease progression, early disease treatment data, primary care education to reduce delays to diagnosis @RheumNow
sheila
Tweet
Roc-SpA study
Active axSpA dse + inad response to TNFi ➡️switch or cycled
No significant diff in ASDAS40 at wk24 bet IL-17i & 2nd TNFi
Switching to IL-17i not superior to cycling to 2nd TNFi after inad. response to 1st TNFi
Shared decision is key
AbsOP0235 @RheumNow #EULAR2026 https://t.co/3UP37IEgXv
#OP0236: a look at the revised 2025 ASAS-SPARTAN classification criteria for axSpA from the global CLASSIC cohort. The updated criteria achieved 79.5% sensitivity & 90.4% specificity, with MRI & radiographic sacroiliitis remaining central to classification. #EULAR2026 @RheumNow https://t.co/rVIqyCmB8K