The opening of ACR2 Convergence was a hit for all who signed up and viewed in. The day included the presidential address by outgoing president Dr. David Karp (UT Southwestern) and a keynote talk and interview with Dr. Seema Yasmin (Stanford).

All News
Article
Article
Growing awareness of spondyloarthropathies over the last two decades has led to a better understanding of the pathophysiology of spondyloarthritis, and subsequently increased interest in more distinct, disease state specific treatment options.
Article
Giant cell arteritis is associated with significant treatment related morbidity due to the dependence on glucocorticoids as a treatment option. After sixty years of therapeutic stagnation, these are exciting times in the management of GCA. At this year's ACR Convergence meeting, encouraging data will be presented on options for GCA.
Aurelie Najm
Tweet
ORAL surveillance TOFA vs. TNFi:
in patients with > 50yo > 1 CV risk MTX IR
-# ⬆️ in MACE and MI (not stroke)
-MACE risk factors on TOFA smoking, >65 male gender
-# ⬆️ MACE in its w/ any of these RF
What are you going to tell your patients? #Abtr0958 #ACR21 #ACRBest @RheumNow https://t.co/81kVTH63bb
MACE risk Tofa vs TNFi ORAL surveillance: age 50+ w/1 additional CV risk, MTX-IR
👉higher # MACE, MI in Tofa 5 or 10 mg bid (no increase in stroke)
👉risks for MACE w/tofa: tobacco, ASA, age 65+, male sex
👉counsel high risk pts (?avoid use)
Abst#0958 #Plenary #ACR21 @rheumnow https://t.co/tg35cts9tw
Janet Pope
Tweet
Oral Surveillance outcomes in a nutshell Tofacitinib two doses vs TNFi event driven trial more AEs of interest in Tofa groups MACE Malignancy SIE in older groups VTE esp #tofacitinib 10 mg BID @RheumNow #ACR21 #ACRBest abst#0958 https://t.co/j39g7yVVFB
1133 MACE events in Oral Surveillance study - Tofa use in high risk pts had more MACE events than TNFi use. Abstr# 0958 #ACR21 Problems with the gimmish are:
- Older patients, w/ Hi CV Risk
- 50% prednisone use
- Use of TNFi as comparator (effective at lowering CV risk) https://t.co/lzIyhgzvRe
⭐️IR for MACE, MI, non-fatal MI numerically ⬆️ in Tofa vs. TNFi
⭐️HR for MACE/MI/stroke >1 for Tofa vs. TNFi
⭐️Risk factors: Smoking, ASA use, Age>65, men
⭐️Pts without risk factors, IR for MACE were similar
Abs#958
#ACR21 @RheumNow #ACRBest
https://t.co/xA3aGu5Sqi https://t.co/VnPHBhrmdx
David Liew
Tweet
okay, so let's look at the #ACR21 plenary as we go
so a reminder - FDA-mandated phase 3b/4 safety endpoint study
specifically looking at patients >50yo with at least one other CV risk factor
today we're looking at MACE: that's CV death (excl PE), MI, stroke
ABST0958 @RheumNow https://t.co/9U8Sahb9Q7
2 year extension study on Upadacitinib in active AS
⭐️ASAS40 response maintained
⭐️MRI SPARCC scores decreased and maintained
⭐️infections most common AE
⭐️NO MACE, lymphoma, skin cancer, GI perforations
Abs#924
#ACR21 #ACRBest
@RheumNow
https://t.co/725IRAOgtW https://t.co/FVUoCi6aoQ
Eric Dein
Tweet
#ACR21 Abs#0828. SELECT-COMPARE UPA vs ADA for RA at 3 yrs
⭐️More pts stay on UPA vs ADA (47 vs 36%)
⭐️Adverse drug events similar between groups. UPA has ⬆️ zoster, lymphopenia, hepatic and CPK elevations
https://t.co/eLCytSX7Gz @Rheumnow https://t.co/i8NjSgImVq
Richard Conway
Tweet
And here is ORAL-Surveillance, small increase in MACE and malignancy with tofacitinib vs TNFi. 1 extra MACE per 319-567 patient years, 1 extra malignancy per 275 patient years. Abstr#0831 #ACR21 @RheumNow https://t.co/wMJnspTTBy
David Liew
Tweet
For rheumatologists, instinct says in RA everything’s better with MTX. For tofacitinib, where immunogenicity not an issue, is that actually true?
Canadian registry data: maybe no
after 36m, low no. ?valid, markups mine
Need to see more of this!
#ACR21 ABST0827 @RheumNow https://t.co/VVwd4SZgVx
Richard Conway
Tweet
3 year results of SELECT-COMPARE study of upadacitinib. No evidence of a signal in cardiovascular events or cancer. Reassuring, but really need an ORAL-Surveillance style study of upadacitinib to be confident. Abstr#0828 #ACR21 @RheumNow
David Liew
Tweet
So it's day 2 at #ACR21, and you know what that means - it's ORAL Surveillance day!
This is the figure everyone will be talking about, leading up to details in the plenary.
Why are the other bars higher than the pink bars?
ABST0831
plenty of @RheumNow coverage coming on this https://t.co/B80cSmhNV7
David Liew
Tweet
ORAL Surveillance
In mod-severe RA pts >50yo, with CV RF & no hx malignancy, patient-years of exposure required for one event (vs TNFi):
MACE
tofa 5mg bid: 567
tofa 10mg bid: 319
malignancy
tofa 5mg bid: 276
tofa 10mg bid: 275
#ACR21 ABST0831 @RheumNow https://t.co/9vyXPTMFzj
Great start to #ACR21 and great recap of the year in rheumatology.
Positive data on tofacitinib and AS but still pending approval.
Where would JAKinibs be in your AS treatment algorithm?🤔
@RheumNow https://t.co/cs8U33355A
Richard Conway
Tweet
Tyk2/Jak1 inhibitor brepocitinib in PsA. Looks good. Works for skin, joints, enthesitis, dactylitis, and PROs. No unexpected safety signals. Abstr#0488 #ACR21 @RheumNow https://t.co/MIOLw8BABN
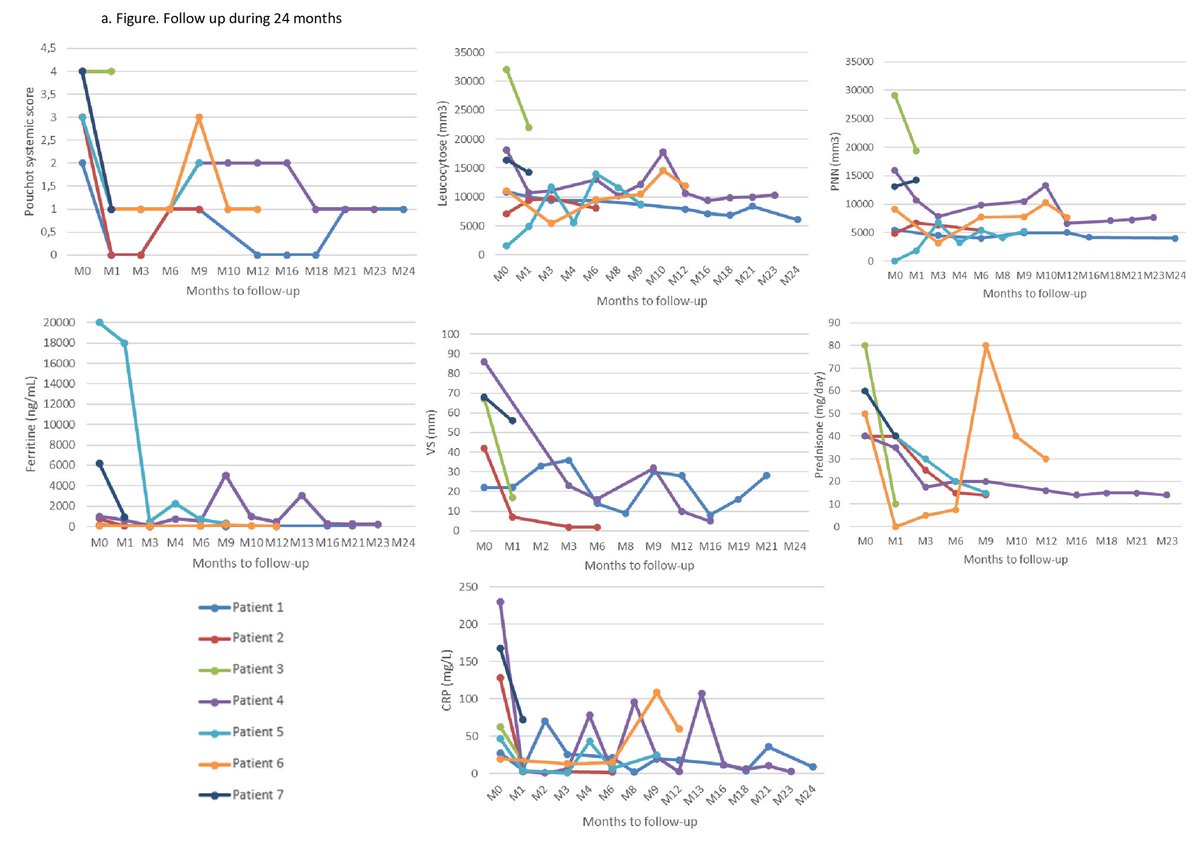
@RheumNow #acr21 abst 195 prospective study of JAKi for refractory Still’s in 7 pts suggests JAKs can be useful as an add on but not in monotherapy : partial response 57%& failure in43%. No patient achieved complete remission. steroids could be decreased by63%~ https://t.co/rYHVReRHvL
The evolving JAK inhibitor story
Black box Warnings regarding JAK inhibitor use and MACE, malignancy, thrombosis and mortality - full safety data remains to be examined.
@ACRheum #ACRambassador #ACR21 https://t.co/imQ1LSxeXM