We’ve recognized the increased risk of cardiovascular disease (CVD) in SLE for almost half a century since Urowitz et al. first described a bimodal pattern of mortality in lupus patients in 1976. Numerous subsequent studies have confirmed this, with estimates of increased risk ranging from 2-10-fold compared to the general population. Most striking is the risk in young patients; in their landmark study, Manzi et al. found that women with SLE in the 35–44-year age group had an almost 50-fold increased risk of myocardial infarction compared to age-matched women without SLE.

All News
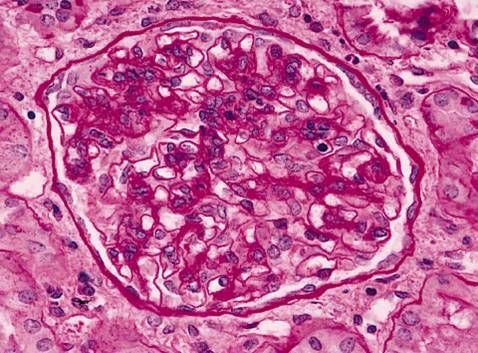
The full house immunofluorescence pattern is the classic histopathologic finding of lupus and lupus nephritis. Glomerular deposits staining for IgG, IgA, IgM, C3 and C1q can help confirm a suspected diagnosis of SLE. But what about patients with negative immunofluorescence and no proliferative or membranous features?
Attendees at the 2025 RheumaPreg meeting were excited to discuss the newly released EULAR recommendations for use of antirheumatic drugs in reproduction, pregnancy, and lactation. Table 1 summarizes the major recommendations from EULAR (2025) and the American College of Rheumatology (2020) reproductive guidelines for commonly used medications in SLE. It should be noted that these two sets of guidelines largely align, however, the updated EULAR guidelines have included some additional medications incorporating data from the last five years.
Comparing EULAR (2025) and ACR (2020) Guidelines on Safety of Lupus Medications in Pregnancy Attendees at the 2025 RheumaPreg meeting were excited to discuss the newly released EULAR recommendations for use of antirheumatic drugs in reproduction, pregnancy, and lactation. https://t.co/DSYPaElRij