Today the US Food and Drug Administration (FDA) approved secukinumab (Cosentyx) for the treatment of adults with polymyalgia rheumatica (PMR) who have had an inadequate response to corticosteroids or who cannot tolerate corticosteroid taper.

All News
Article
Article
Steroids remain both the cornerstone and the Achilles' heel of PMR management. We have aspirations of briskly tapering our patients once they have had their honeymoon phase with prednisone. But when Ms.
PMR: Spare The Steroids Please
Steroids remain both the cornerstone and the Achilles' heel of PMR management. We have aspirations of briskly tapering our patients once they have had their honeymoon phase with prednisone. But when Ms. Jones calls you with a reported second PMR https://t.co/dbrdVZRuoN
David Liew
Tweet
Great @RheumNow Day 2 Daily Recap today talking about trends in SpA therapy, PsA and obesity, gout flares and CV risk, IL-17/23 in PMR/GCA, and as always a healthy dose of 'AI is coming/here'. All the good stuff from #ACR26 with @synovialjoints @AdelaCastro222 @ericdeinmd https://t.co/FSjr2Qn3JC
David Liew
Tweet
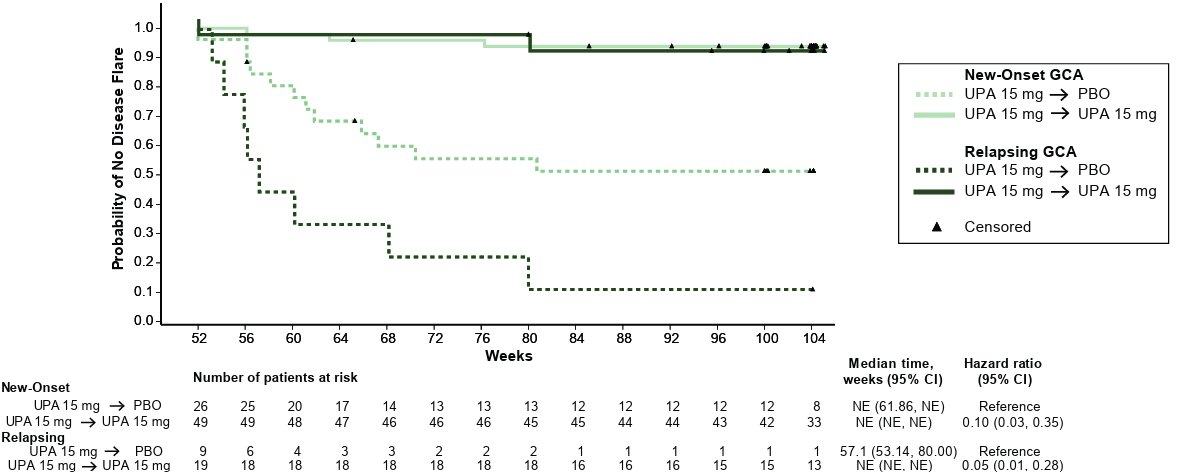
We do GCA studies with new-onset & relapsing data mixed in, for practical purposes.
Yet this is a sometimes phasic disease
in SELECT-GCA (upadacitinib), those randomized to stop upa at 52w relapsed far less if new-onset (vs prev relapsing)
*different*
ABST2122 #ACR26 @RheumNow https://t.co/NMOIBONjar
Richard Conway
Tweet
He et al. Tofacitinib + 4 weeks GC vs standard GC in PMR. Equal efficacy. Far less steroids, and less diabetes and osteoporosis in tofa group. @RheumNow #ACR26 Abstr#2106 #ACRbest https://t.co/acH8RauYln
David Liew
Tweet
Wondering what you would use cheap generic tofacitinib for?
Well look no further. Find someone who would rather take steroids over tofa for their PMR & I will take them to meet my patients.
ITTG PMR study (open label RCT, n=104)
same people as EAST PMR
ABST2106 #ACR26 @RheumNow https://t.co/VQh1zprZbC
Janet Pope
Tweet
What happens in #PMR after d/c #secukinumab post 1 yr #Rx?
Pts flare
#secu 300mg flare 44%
Secu 150mg 43%
PBO 61.5%
Time to flare more prolonged by 2 mo post 300mg secu withdrawal
#ACR26 #1893 @ACRheum
@RheumNow
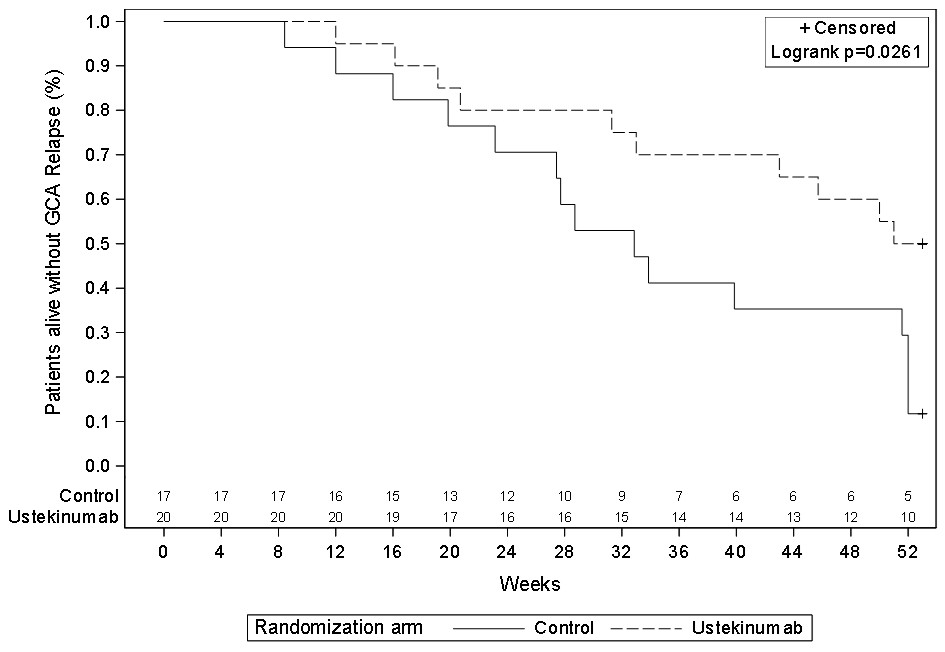
Ustekinumab in GCA contradicts other similar small studies of similar design
38pt open label RCT of UST in GCA; pts who recevied UST had higher rate of primary composite (alive, sustained remission, cumulative pred within 10% of plan), 45% vs 12%; p=.028.
That's great, but https://t.co/gAvUAan4b3
Richard Conway
Tweet
Dua et al. Sarilumab vs MTX in PMR. Retrospective claims based study. Outcome = median days to glucocorticoid discontinuation, Sarilumab superior to MTX. @RheumNow #ACR26 Abstr#1895 https://t.co/868B6vuYk4
High rate of PMR relapses post treatment withdrawal
REPLENISH (RCT of SEC vs PLBO in PMR) post hoc study followed pts AFTER 52 week period ended (ie both arms off therapy)
Relapse occurred in 43% in SEC vs 62% in PLBO; relapse free survival longer with SEC, even w/all pts OFF https://t.co/DfQWj6mMKB
Richard Conway
Tweet
Maslyanskiy et al. PROMISE trial in PMR. IL-6i olokizumab. @RheumNow #ACR26 Abstr#1127 https://t.co/4xVUuPtsmr
Brian Jaros, MD
Tweet
Secukinumab reduces steroid toxicity in PMR
Additional results from REPLENISH:
Lower glucocorticoid toxicity scores across ALL domains by week 52 compared to PBO
SEK is effective for PMR AND reduces need for steroids... when will we get approval?
#Abst1145 @RheumNow #ACR26 https://t.co/bLjydtTDRA
How should guidelines for #GCA be developed to reflect what matters most to those affected?
@KKouranloo presents a national mixed-methods study exploring stakeholder-informed priority setting for UK GCA guideline development.
@RheumNow #ACR26 https://t.co/ufdPN55Mdz
Richard Conway
Tweet
Schmidt @Janetbirdope et al. Post-hoc SAPHYR analysis showed significantly higher remission when sarilumab was initiated within 6 months of PMR onset @RheumNow #ACR26 Abstr#0167 https://t.co/b0xPwYK0E5
Richard Conway
Tweet
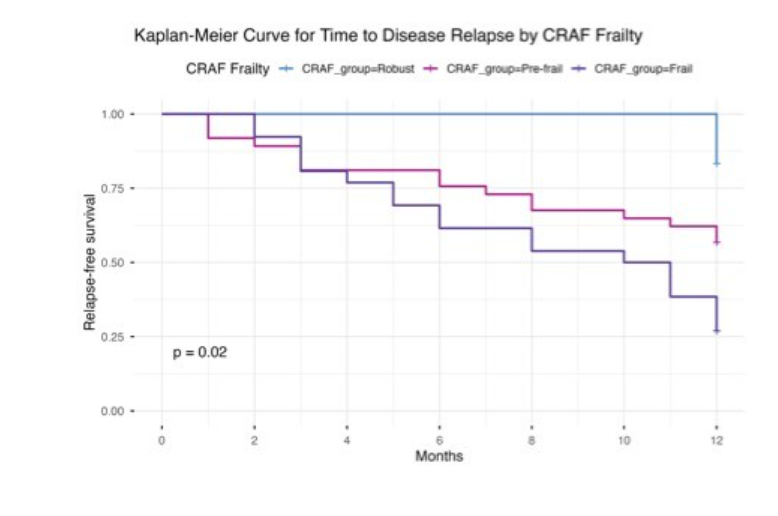
Harkins @DrTrishHarkins et al. Comparison of frailty tools in PMR. Different tools have different strengths, choose based on outcome of interest - CRAF for relapse, SHARE-FI infection risk. @RheumNow #ACR26 Abstr#0164 https://t.co/Vh6zxzsncR
Brian Jaros, MD
Tweet
Normal CRP does NOT exclude GCA
Abst0172 compares low & high CRP GCA patients
Low CRP pt:
- less systemic symptoms
- less PMR
- MORE vision sx and stroke
- lower relapse risk
We are in desperate need of better GCA biomarkers, especially with vision risk
@RheumNow #ACR26 https://t.co/83hE0tbpvG
Brian Jaros, MD
Tweet
We should be using steroid-sparing therapy in PMR EARLY!!
Analysis of SAPHYR: better response to Sarilumab compared to PBO extinguished in patients with disease longer than a year
A similar trend was observed in a comparative real world data set
Abst0167 @Rheumnow #ACR26 https://t.co/OO5Nv3DJZd
David Liew
Tweet
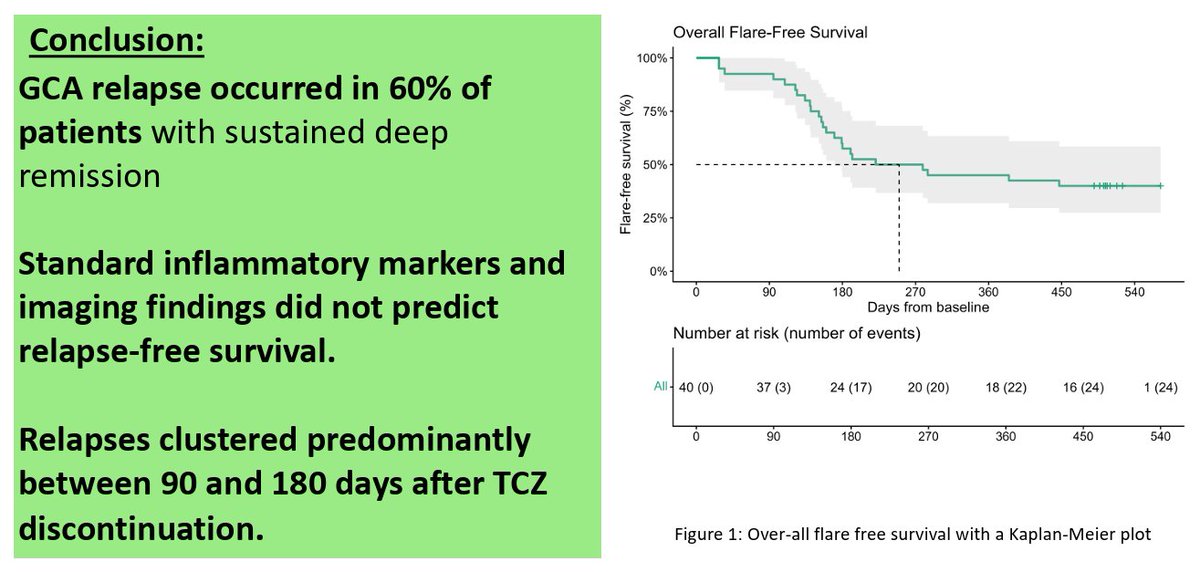
If your longstanding GCA is asymptomatic, has normal imaging & labs on tocilizumab, can you stop TCZ without flare?
Erlangen n=40
very stable on TCZ (mean disease 2.9y, TCZ Rx 1.9y, remission 1.4y)
over half still flared
There are no guarantees in GCA
ABST0186 #ACR26 @RheumNow https://t.co/syuN3tnPk3
Year in Review Top Awardees: PMR/GCA (Stone, NEJM 2026)
Phase 3 DB RCT, 28 countries, n=381
Secukinumab 300 vs 150 mg vs PBO + GC taper
Sustained remission wk 12 to 52: 41% (both doses) vs 20%
Annual GC ↓ ~410-490 mg.
Approved in EU, US pending
@RheumNow #ACR26 https://t.co/6RT5yKIoIF