Most patients with rheumatoid arthritis (RA) whose initial treatment used a stringent treat-to-target strategy in a clinical trial were in remission 10 years later, with only modest radiographic progression over that time, researchers said.

All News
Article
Article
As the leaves start changing color and spooky decorations populate neighborhood doorsteps, another autumnal tradition begins: vaccination counseling. Fall offers a golden opportunity to protect our patients before respiratory viruses fill our waiting rooms. In patients with rheumatologic diseases, vaccinations can be confusing and worrisome. For clinicians with limited bandwidth, these conversations can feel like added responsibilities in an already overfull schedule.
Article
Dr. Jack Cush reviews this week's news from RheumNow.com, including: placebo trumps controversial therapies, the dynamics of disease activity, fuse the big toe, and patients don’t appreciate being told “it's all in your head”!
Tis the Season for Vaccination
Vaccination is essential for all rheumatologic patients, but particularly for patients on glucocorticoids and immunosuppression who face increased risk from infectious diseases.
https://t.co/hHx1okkwHD https://t.co/nzRa9pzQ1X
Cryptococcus is rare, but twice as likely with JAK inhibitors. Retrospective TriNetX analysis of RA pts (>30k/grp) starting JAKi vs TNFi; JAKi vs non-TNFi; & TNFi vs non-TNF. Crypto seen in <0.2% in all groups; but signif higher HR for JAKi (HR 2.2 & 2.15) https://t.co/fJeKwDZABL
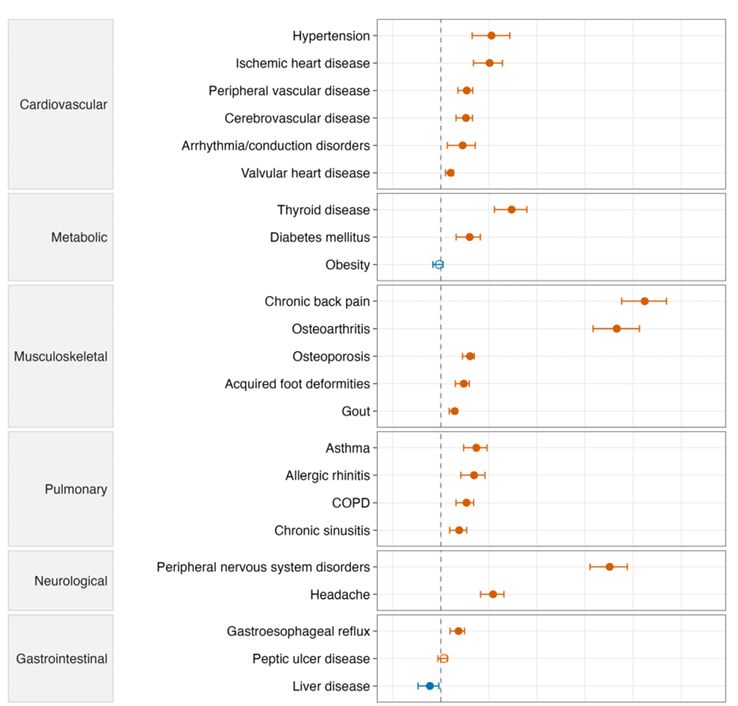
Polish study compared comorbidities #s in incident RA & PsA. RA pts were older at dx (61 vs 44 yrs) & may drive higher rates in RA. 23/3 comorbidities (74%) were signif more prevalent in RA, including HTN (18 v 12%), ischemic HD (11 v 6%), cerebrovascular dz (4 vs 2%) https://t.co/l0RW6bVVHd
No difference in MACE risk betw TNFi vs JAKi in 6174 RA pts. Korean claims data compared TNFi (n 5,152) vs JAKi (n 1,022) initiators. MACE risk was 4.1 & 3.6/1000PYs w/ TNFi vs JAKi, respectively. MACE risk did not differ significantly between JAKi and TNFi (adj HR 0.636; 0.283, https://t.co/035WSUQAhJ
Placebo beats probiotics in PsA. And nearly 90% of well-controlled RA patients may be able to cut their targeted therapy dose in half.
Dr. Jack Cush breaks down the findings worth a closer look in this week's RheumNow podcast, Troubles with ‘Gut Feelings’.
Probiotics in PsA: https://t.co/Aqy4HxGHbU
Italian GISEA (early RA) registry = 1304 pts Rx w/ JAK inhibitors. Retention rates at 6, 12, & 24 mos = 81%, 75%, & 61%. Low retention w/ baseline GC, high Dz activity, & pain. https://t.co/kKZmTHmEUb https://t.co/JlUUrFIU4G
Can DMARD Doses Be Safely Reduced for RA Patients?
Close to 90% of patients with rheumatoid arthritis (RA) well controlled on targeted therapies were able to take 50% dosage reductions without experiencing worsened disease activity in a randomized trial, South Korean https://t.co/MyjZdRaGb4
In early RA, initial b/tsDMARDs are better than MTX. Metanalysis of 29 RCTs (13387 pts), Vs MTX alone, initial b/tsDMARDs + MTX signif incr DAS28 remission 2 6 mos (RR 1.62) & 12 mos (RR 1.54). Benefits greater w/ higher baseline Dz, seropositivity https://t.co/exwVOc08xR https://t.co/00UXGTGPaH
Study of Prognostic Nutritional Index (PNI) in 984 RA pts shows PNI is independently inversely corelated w/ RA dz activity, esp. PNI <45. PNI = ser albumin & lymphocyte count calculation (10 × s albumin [g/dL]) + (0.005 × lymphocyte count/mm³]). Other studies have shown modest https://t.co/AV3AGXwSfg
French National Health System study of 214,892 #RA pts (~40K on TNFi) found 562 demyelinating events (2008-2023) w/ cumulative 10 yr incidence of 0.32% w/ csDMARDs & 0.50% w/ TNFi (HR 1.47;1.11-1.95). Demyelinating events are rare in RA, but signif higher w/ TNFi https://t.co/6vUy5nsQ27
On this week's podcast, Dr. Jack Cush reviews the news: Steroids are easy to start and hard to stop; hold the MTX but not the biologic or JAK, weighing in on avacopan, and age-old messages for old-age patients.
🎧 Read + listen: https://t.co/kK8WKgIxYT and subscribe wherever you https://t.co/xGTXyuRJU8
? value of FamHx in Rheum evals? My bias is that few Dz are heritable - #Ank Spondylitis, #gout, DIP Osteoarthritis! But literature says there's high heritability for SLE, RA, systemic sclerosis, Sjögren's, & autoimmune endocrinopathies. WHAT do you think? https://t.co/WGyQqpY1qX
Can DMARD Doses Be Safely Reduced for RA Patients?
Close to 90% of patients with rheumatoid arthritis (RA) well controlled on targeted therapies were able to take 50% dosage reductions without experiencing worsened disease activity in a randomized trial, South Korean https://t.co/GGPOBhVhJe
Not all Low Dz Activity RA pts do the same. COREVITAS study of 6,856 RA pts w/ baseline CDAI 0-10. Comparing very low LDA (2.8-6: ~19.6%) vs high LDA >6-10 (31%);latter were twice as likely to have CDAI moderate Dz activity at 1 and 2 years https://t.co/mmc1wzJXWY https://t.co/5CotYBn0Zb
In early RA, initial b/tsDMARDs are better than MTX. Metanalysis of 29 RCTs (13387 pts), Vs MTX alone, initial b/tsDMARDs + MTX signif incr DAS28 remission 2 6 mos (RR 1.62) & 12 mos (RR 1.54). Benefits greater w/ higher baseline Dz, seropositivity https://t.co/exwVOc08xR https://t.co/Zcl62rxxJk
T-cell engager blinatumomab (CD3xCD19 TCE) was used for Deep B-cell depletion in 15 resistant RA pts (MDR-RA). @wk 12 9/15 CDAI LDA, 3/15 CDAI remission. Synovial B cells were depleted (4 of 5 biopsies) but not in lymph nodes. Later, 14/15 flared. No ICANs, 3/15 w/ CRS (gr 1) https://t.co/xLGZjkMmit
Retrospective Kuwait registry study of 2629 RA pts- 2326 (88.5%) w/ early (EORA) vs 303 (11.5%) late(LORA). LORA had more age related comorb. Dz (2 vs. 0.9), similar DAS28/CDA, but signif higher ESR (41 vs 33). T2T applies regardless of age!! https://t.co/MK8SfjcxCA https://t.co/ZxHwt8qxvT