The final day (day 4) of the ACR 2020 meeting saw a flurry of late-breaking abstracts and other novel studies that excited our faculty. Below are some of their choices for #ACRbest.

All News
Article
Article
Rheumatology Round-Up tonight 8:00pm EST, 7pm CST. Drs. Artie Kavanaugh and Jack Cush reprise their long-running end of ACR highlights. Rheums can watch by Zoom (Q&A too), everyone can watch on RheumNow.com or our YouTube channel. See you there!

Meral K. El Ramahi, MD
Tweet
Summary of #ACR20 part A:
- HCQ is not a problem in rheumatic dz pts in terms of causing QTc prolongation
- Anti-phospholipid ab are found in a majority of hospitalized COVID19 pts — the most prevalent of which were anti-PST abs that are not in the of criteria for APS
@rheumnow
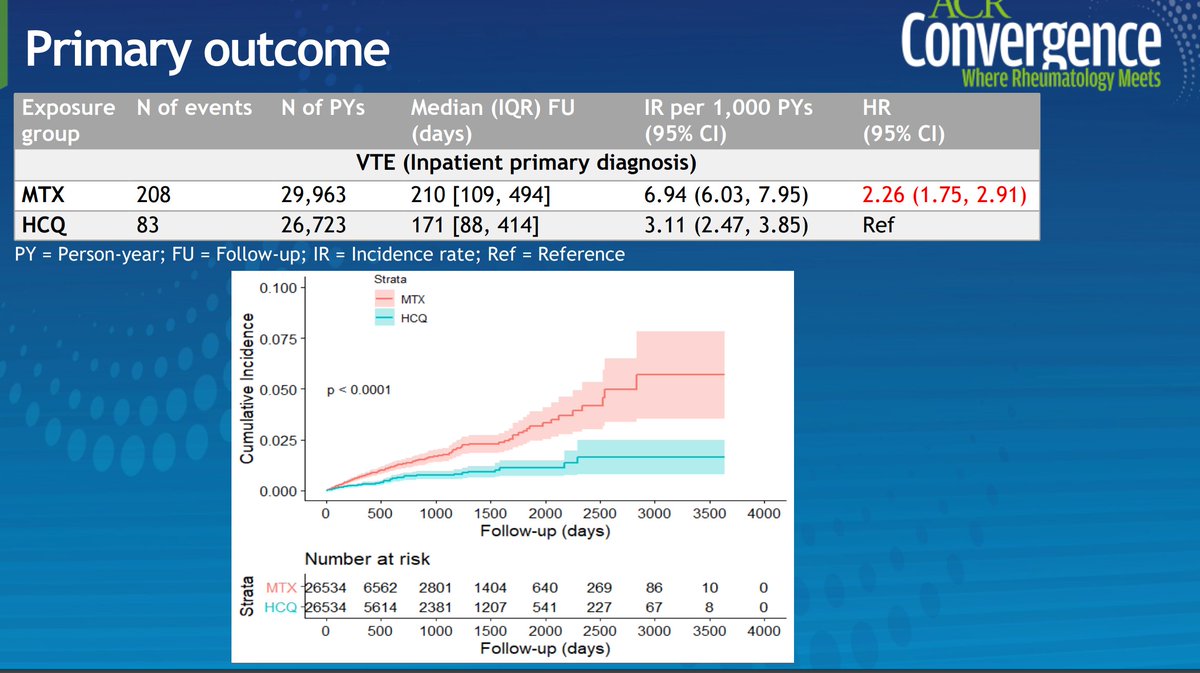
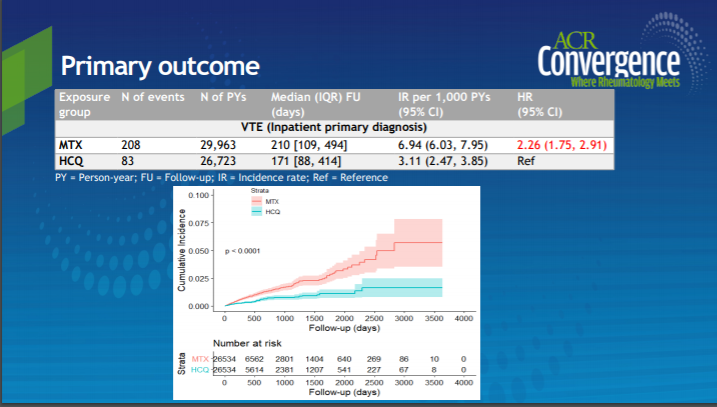
Abst#2000. PRIME team Medicare database study pts with new RA started on MTX higher VTE risk than HCQ (HR 2.3). Unable to assess disease activity because claims database, but would imagine MTX grp more severe, driving increased VTE risk @RheumNow #ACR20 https://t.co/Z14xFTVXTp
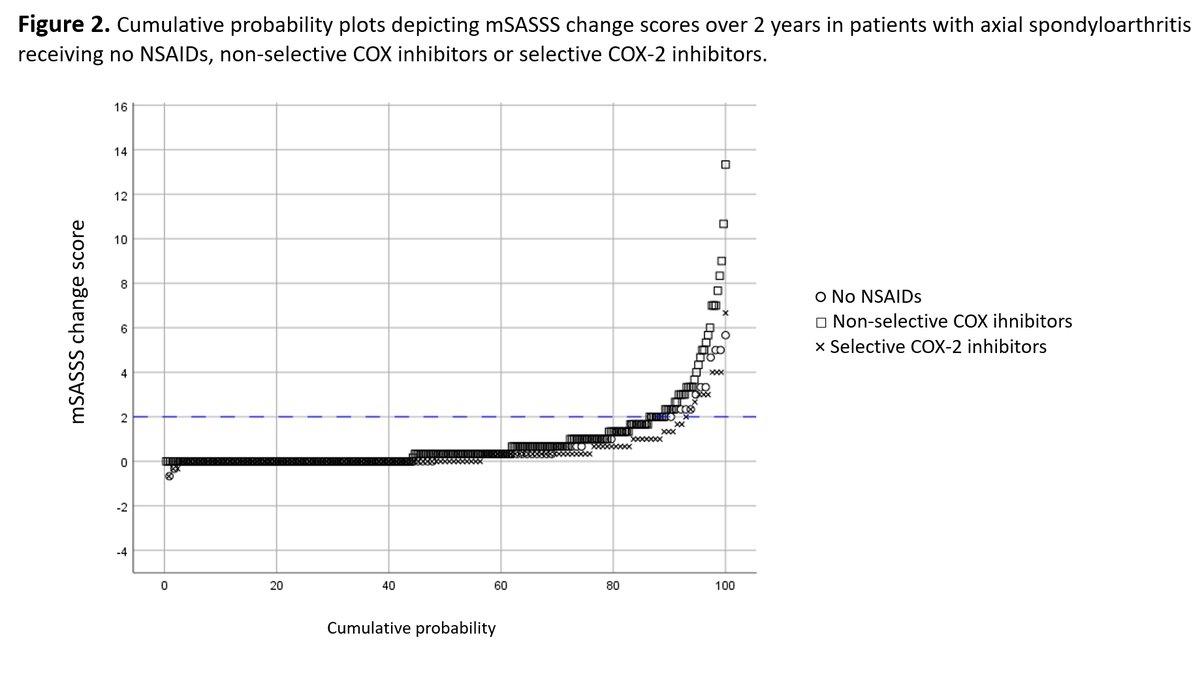
COX2 inhibitors associated with inhibition of radiographic spinal progression in AxSpA pts compared to non-selective NSAIDs.
⬇️radiographic spinal progression over 2 yrs
⬇️mSASSS progression
@RheumNow #ACR20 Abs#2030 https://t.co/p1CeNBm3ma
Late breaking: in older #rheumatoidarthritis patients, those taking MTX have 2x risk of #VTE compared to those on HCQ. Important to consider #thromboembolic risk factors when starting new RA treatment.
Abs#2000 #ACR20 @RheumNow
https://t.co/lt8xDT4Ne8
sheila
Tweet
Large cohort of older RA pts newly rx w/HCQ or MTX:
👉~2-fold ⬆ risk of VTE – both PE and DVT- among patients newly treated with MTX vs. HCQ.
@RheumNow #ACR20 abs#2000 @DanielHSolomon https://t.co/ZnDuMhTMYF
sheila
Tweet
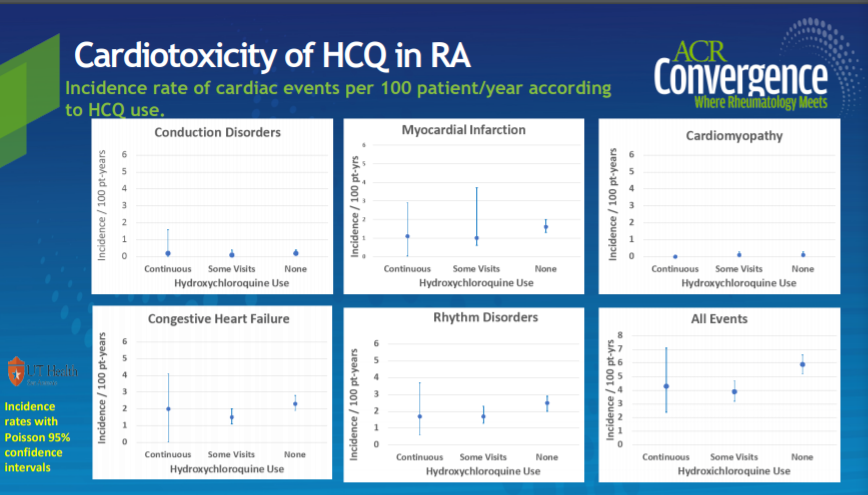
HCQ not associated with ⬆ incidence of cardiac dse in this cohort of RA pts.
We should continue using it. Benefits >>>risks.
@RheumNow #ACR20 abs1999 https://t.co/zYpbX0CsR1
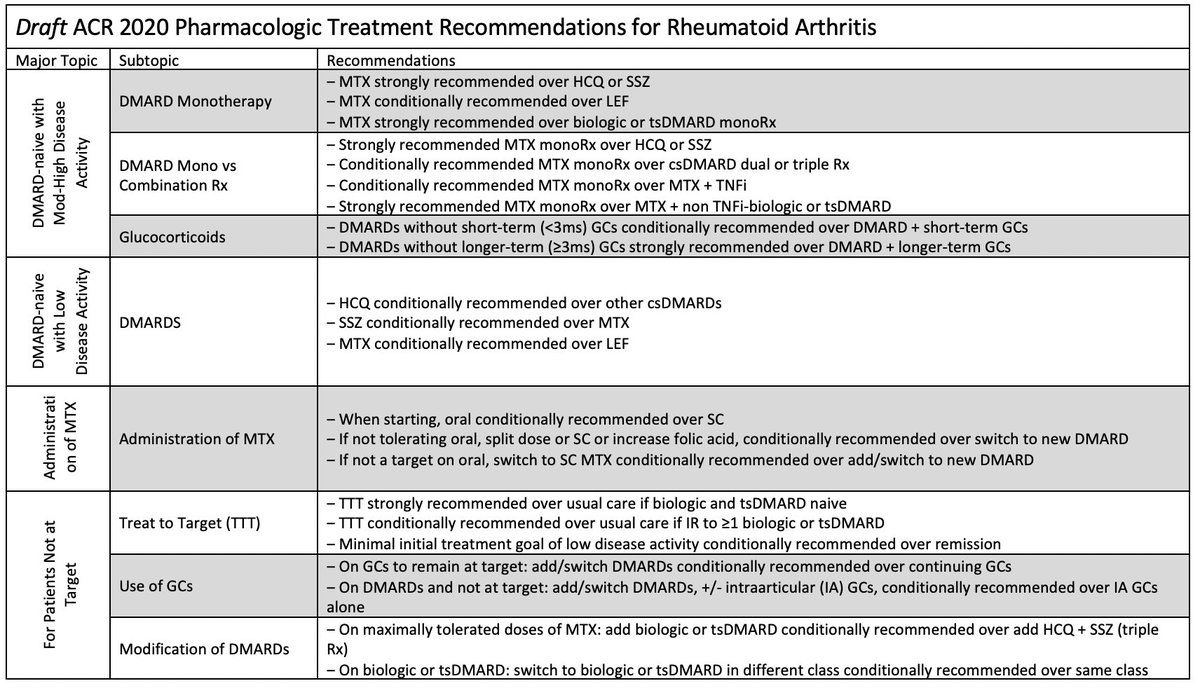
NEW ACR2020 Draft Guidelines for the Pharmacologic Treatment of RA
All the guidelines in 2 tables!
1. MTX 1st, oral > SC
2. Minimize GC!
3. TTT TTT TTT
4. Biologic/tsDMARD > Triple Tx
5. Taper MTX 1st
Close to my practice; suspect will be controversial!
#ACR20 #ACRambassador https://t.co/iFSlq1H65V
Meral K. El Ramahi, MD
Tweet
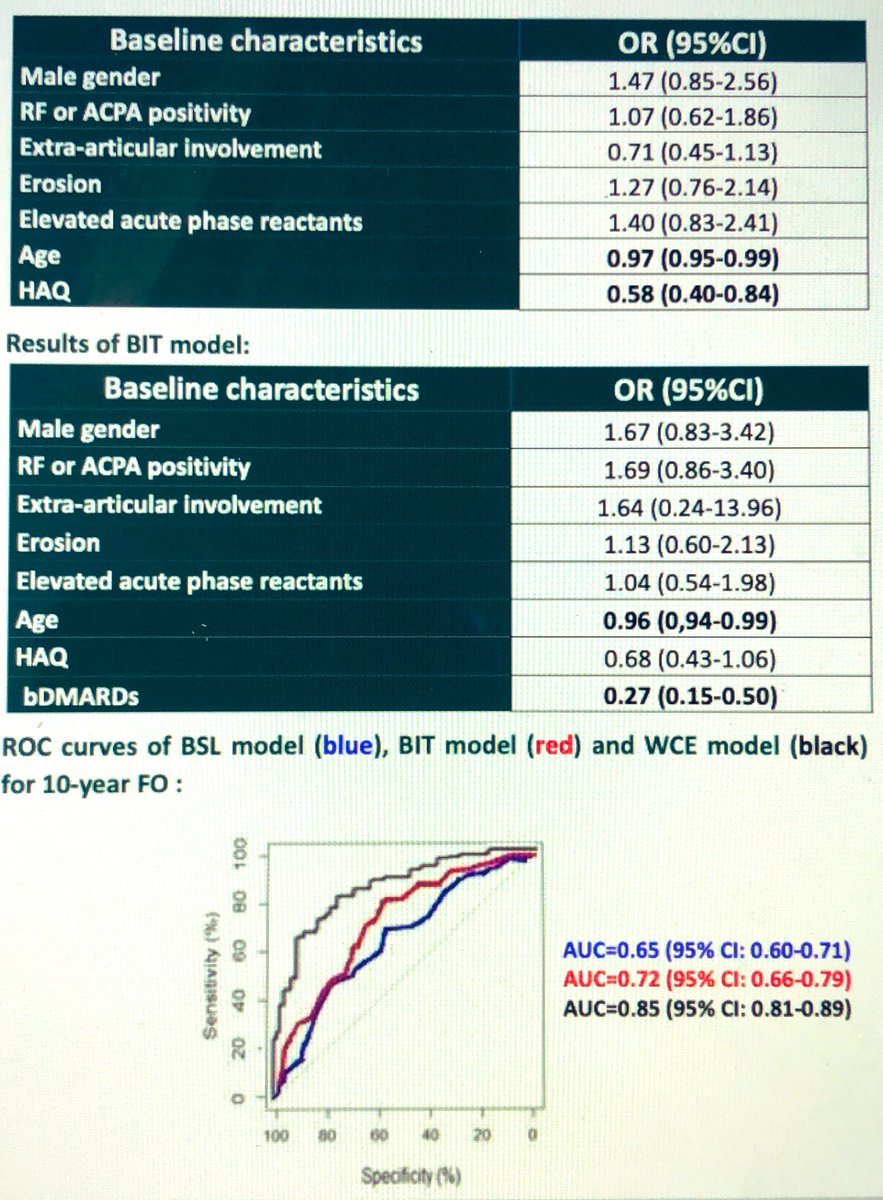
Abst#1717 confirms that early start of csDMARDs as 1st line tx & keeping ts/bDMARD as 2nd line tx (or more) is associated w/ a favorable outcome at 10 yrs in the ESPOIR cohort (a French multi-center cohort that followed patients w/ early RA). #ACR20 @RheumNow https://t.co/bzZiShCF97
Patient-physician discordance seen in ~30% #rheumatoidarthritis patients starting #DMARDs
- ↑Patient-reported pain & functional impairment assoc. w/ discordance
- Patient-centric treatment discussions needed to reduce discordance
Abs#1978 #ACR20 @RheumNow
https://t.co/CdlHrBOdy0
Meral K. El Ramahi, MD
Tweet
Switching or adding a DMARD in pts w/ moderate-high dz RA activity & hx of previous serious infection w/in the past 12 mos as opposed to starting/increasing GCs is conditionally recommended per draft recs of new ACR RA treatment guidelines. #ACR20 @rheumnow @CCalabreseDO
Draft #ACR20 Rx Recs for RA: MTX is conditionally recommended with NORMAL LFTs and no advanced fibrosis. Role of HCQ for NALFD has been suggested at ACR, but not enough for mod-high disease activity @RheumNow. https://t.co/QFF3BK1NF0
Draft #ACR20 Rx Recs for RA: on max tolerated MTX - add bio or tsDMARD conditional recommendation over triple therapy (MTX, HCQ, SSZ). @RheumNow. https://t.co/s6fKEW8czc