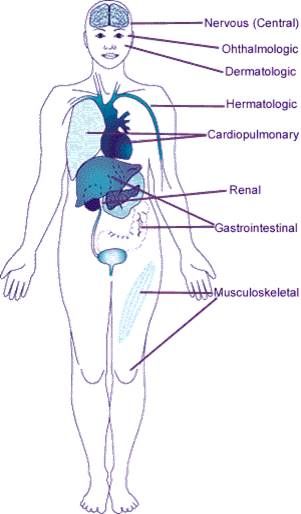
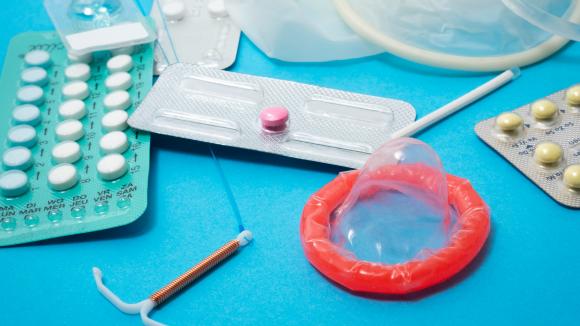
Pregnancy in SLE gets a lot of press in the rheumatology literature, and deservedly so, since pregnancy risks can be markedly increased. It was not that many years ago that women with SLE were counseled to avoid pregnancy.
All News
Nearly 25 years ago, while lecturing on best therapies for rheumatoid arthritis (RA), I loudly stated that hydroxychloroquine was “useless” and, deservedly, I was “boo-ed” off stage. My point then was that rheumatologists needed to be aggressive, if not overly aggressive, in treating all RA patients. And my view was that HCQ was representative of under-treatment. I have reconsidered the use of HCQ in RA substantially in the last few years, based on its merit.
Current guidelines recommend limiting the use of glucocorticoids by coining the new concept of “bridging therapy”, that is, use GCs when the disease is active and get rid of them as soon as you can. This way of thinking is conceptually attractive, however, the formula for translation to real life settings is not included.
A large observational cohort study suggests that monitoring hydroxychloroquine (HCQ) blood levels is effective in systemic lupus erythematosus (SLE) patients with a target therapeutic range (for HCQ level monitoring) of 750-1150 ng/ml.
Dr. Jack Cush reviews the news, journal and regulatory reports from this past week on RheumNow.com. B cell drugs in SLE and ITP, biomarkers in GCA & PSS and great videos by APPs.
The New England Journal of Medicine has published a phase III clinical trial showing that a B cell targeting monoclonal antibody, ianalumab, was effective in more than half of the patients with primary immune thromboc
Dr. Cush provides a systematic approach to evaluating musculoskeletal and rheumatic complaints in clinical practice.
Dr. Jack Cush reviews the news and reports from this past week on RheumNow.com, including reports on FDA resurrections, FM seasonal worsening, and do you fight switch or swap biologics in PsA TNFi nonresponders?