

All News

Maui Potpourri (2.13.2026)
Dr. Jack Cush reviews the hot item takeaways from last week's RheumNow.Live 2026.
Read Article
Obesity, Surgery, and Optimizing Patient Care
Rheumatologic care involves multidisciplinary approaches and collaboration with specialties to treat complex, systemic diseases. While many Pods at RheumNow Live are disease specific, the Pod II focused on Advancing Practice on important and emerging areas affecting rheumatologic patients. This session focused on two major areas of need: obesity and peri-operative management.
Read Article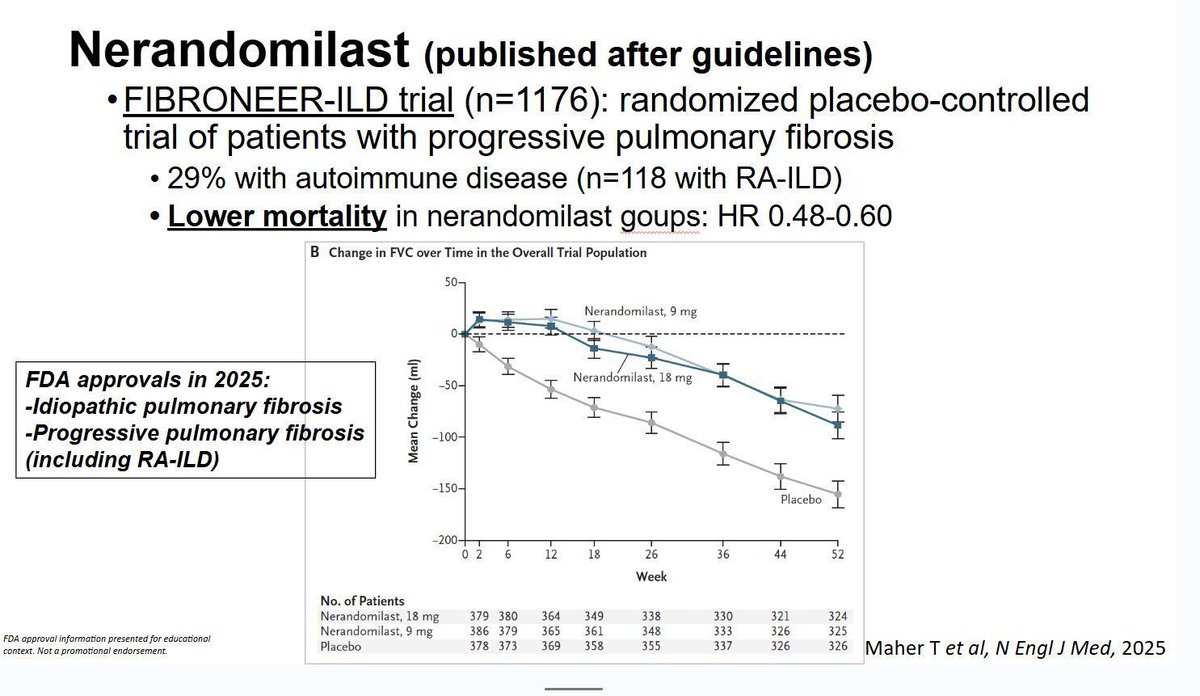
RT @richardPAConway
The new kid on the block in RA-ILD (and other PPF). Nerandomilast, an anti-fibrotic with additional anti-inflammatory/immunomodulating functions. Demonstrated significant mortality benefit in ILD. #RNL26 https://t.co/8DU3WyPQGy
Dr. John Cush RheumNow ( View Tweet)
RT @RichardPAConway
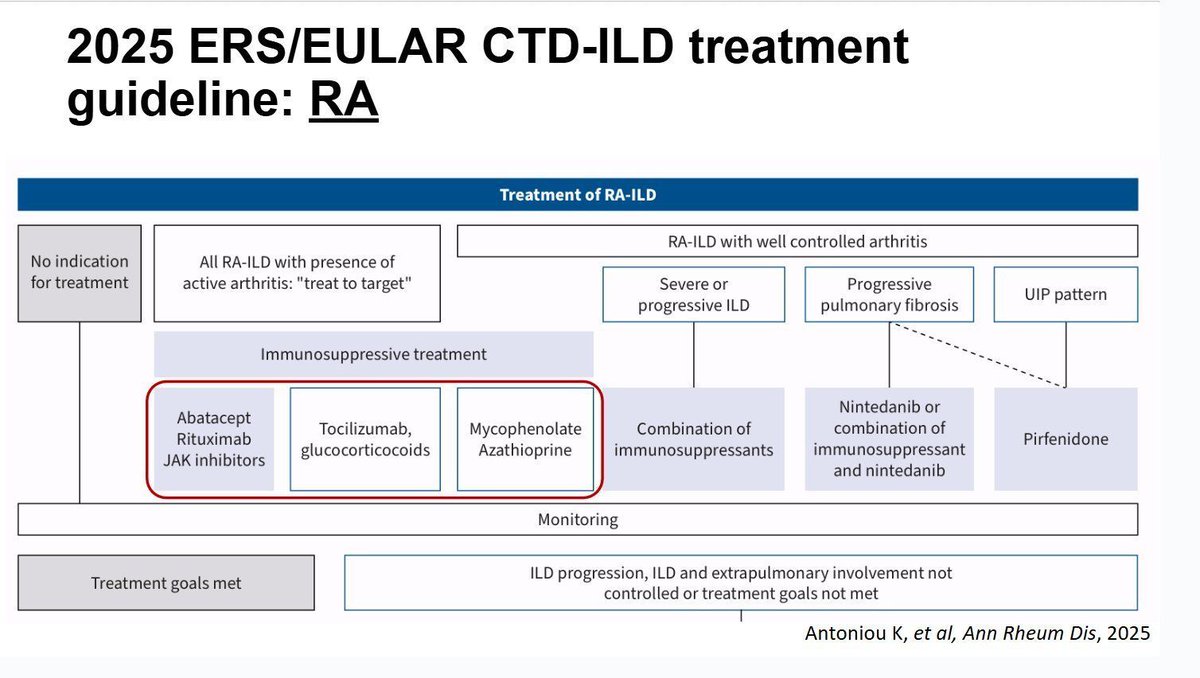
ACR/Chest and EULAR/ERS guidelines for RA-ILD presented by Dr Sparks. I'm posting the one I use ;) #RNL26 https://t.co/a6vwQWbjE7
Dr. John Cush RheumNow ( View Tweet)

RT @ericdeinMD
#RNL26
Prosthetic joint infection vs flare?
- PJI risk 50-80% higher in RA (OR 1.47-1.8)
- Immunosuppressants, intra-artic injections, RA activity, BMI incr risk
- Delay in diagnosis https://t.co/XTozafDQyf
Dr. John Cush RheumNow ( View Tweet)

Screening study of lung US (LUS) vs HRCT in 73 RA pts (DAS28 3.47) Chest HRCT identified ILD in 29%. LUS identified ILD in 22% of patients. LUS sensitivity was 59%; specificity 94%. ROC. This study demonstrates the good diagnostic performance of LUS in RA- ILD detection https://t.co/E8avnbvUiw
Dr. John Cush RheumNow ( View Tweet)

RT @ericdeinMD
#RNL26
Inflammatory arthritis pts getting TKA:
- increased risk of RBC transfusion (OR 1.39), infection (1.64) and readmission (1.46)
- THA: also risk of mechanical complications (like dislocation) OR 1.3 https://t.co/ovW2C2EuXF
Dr. John Cush RheumNow ( View Tweet)
RT @RichardPAConway
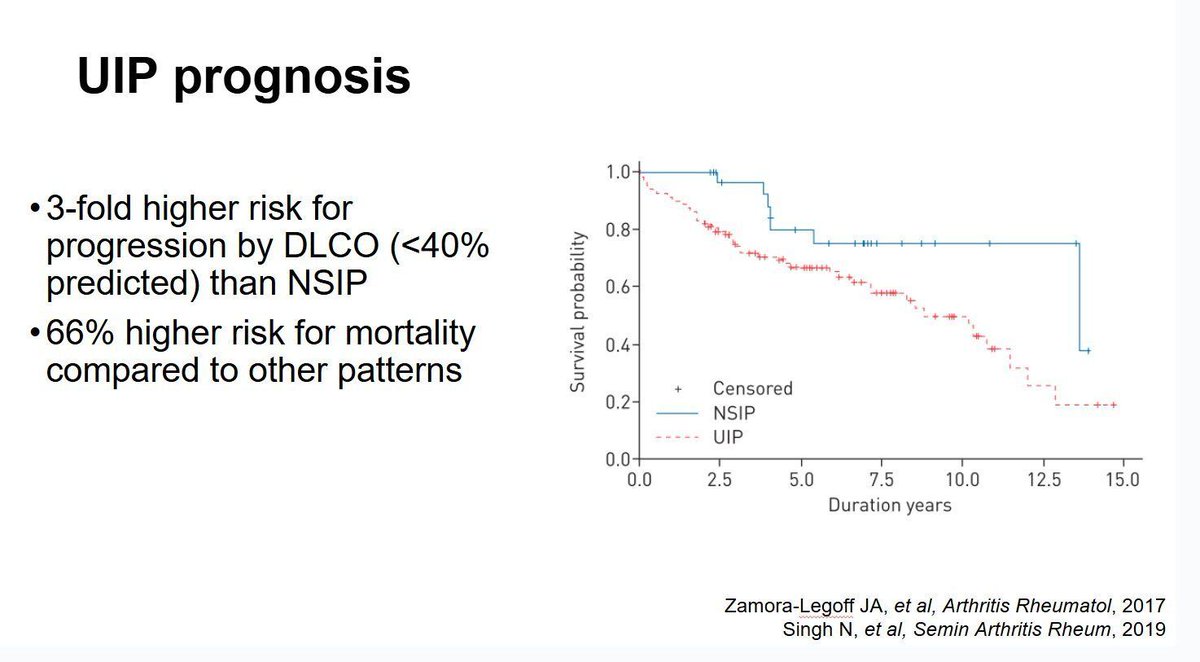
UIP pattern RA-ILD is where the big problem is. We are less good at treating this. Perhaps the newer agents such as nerandomilast will change this? #RNL26 https://t.co/Z0BXxyNrCI
Dr. John Cush RheumNow ( View Tweet)
RT @RichardPAConway
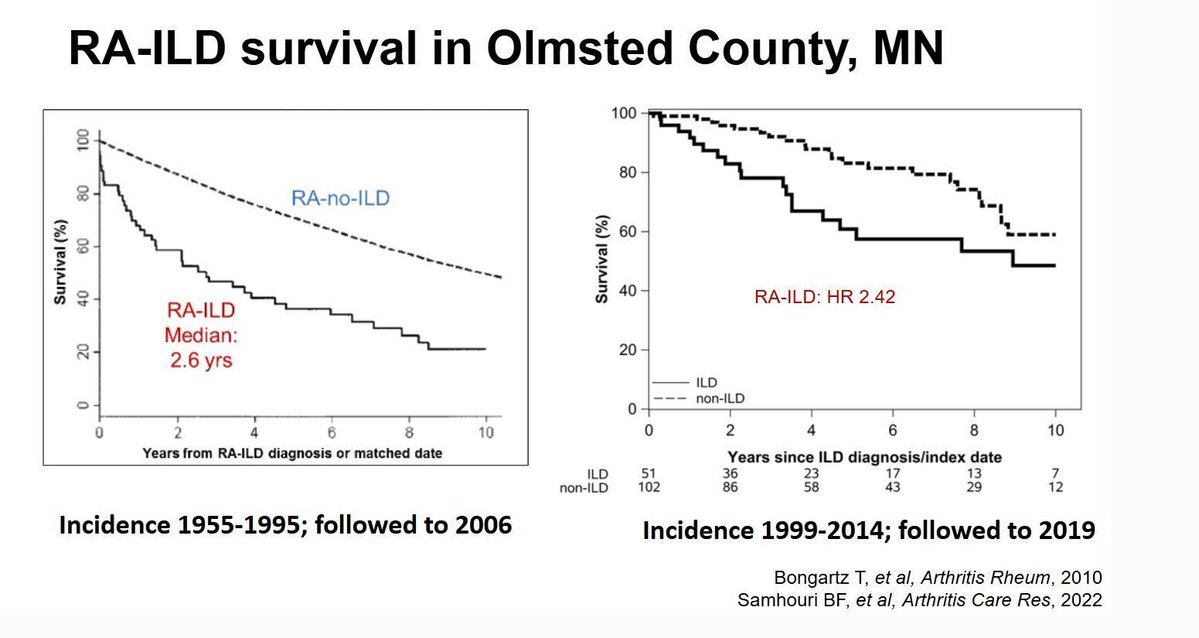
Comparative survival in incident RA-ILD 1955-1995 vs 1999-2014. We are getting better, althoug need to take into account the general survival improvement also. More work to do! #RNL26 https://t.co/VwV33tHgR8
Dr. John Cush RheumNow ( View Tweet)

RT @ericdeinMD
#RNL26 Haque
Effect of GLP1 on Pts with RA
Retrospective study
Significant reduction is RA disease activity (P=0.03), VAS pain (p<0.001), weight, cholesterol and A1c
But 1/3 stopped due to side effects (mostly GI) https://t.co/SNHTcRFmAX
Dr. John Cush RheumNow ( View Tweet)

RT @richardPAconway
We have improved RA mortality in many areas but respiratory (mainly ILD) and infectious issues remain stubbornly elevated. #RNL26 https://t.co/ViucOIOOzY https://t.co/3kIqPMeKKX
Links:
Dr. John Cush RheumNow ( View Tweet)
RT @richardPAConway
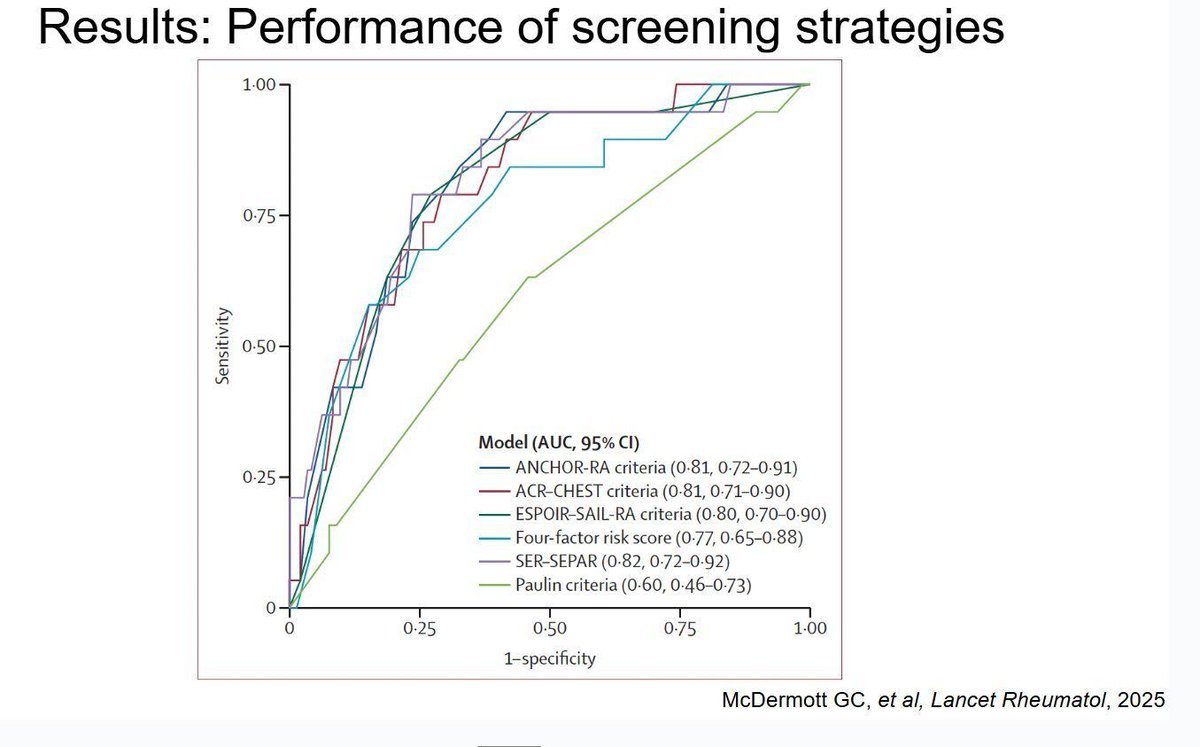
AUC of various published screening strategies for RA-ILD. We often say 0.80 is an acceptable cut off but ideally would like a bit better #RNL26 https://t.co/L19uJ7ETwc
Dr. John Cush RheumNow ( View Tweet)
RT @RichardPAConway
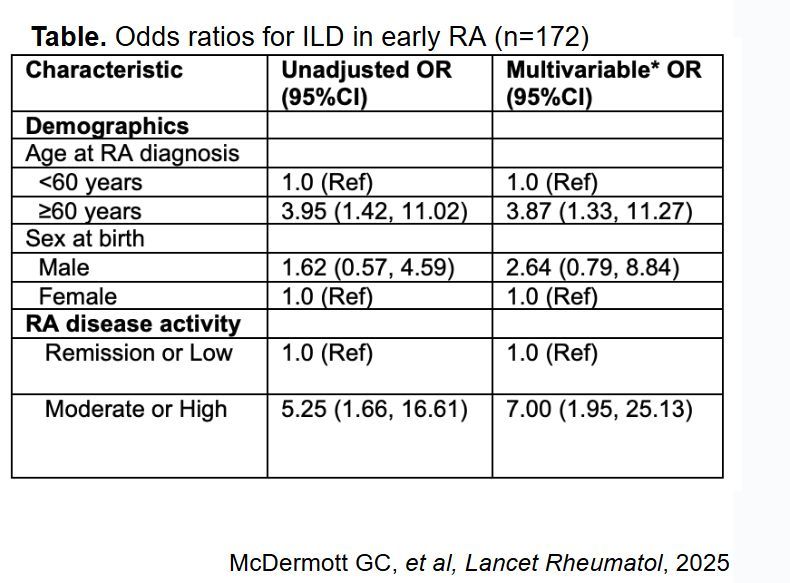
Odds ratios for ILD in early RA from SAIL-RA study. Again disease activity stands out. #RNL26 https://t.co/9cXjOFl3Th
Dr. John Cush RheumNow ( View Tweet)

RT @richardPAconway
Who to screen for RA-ILD is a tricky one. It is not feasible to screen everyone. This is from ACR/Chest 2023 ILD guidelines and is based on identified risk factors. #RNL26 https://t.co/NtAWYCVclJ
Dr. John Cush RheumNow ( View Tweet)

RT @richardPAconway Disease activity is a strong risk factor for RA-ILD. Particularly for moderate/high disease activity but there appears to be a linear relationship (at least above a certain threshold) #RNL26 https://t.co/ot8ttdmu5G
Dr. John Cush RheumNow ( View Tweet)
RT @richardPAconway
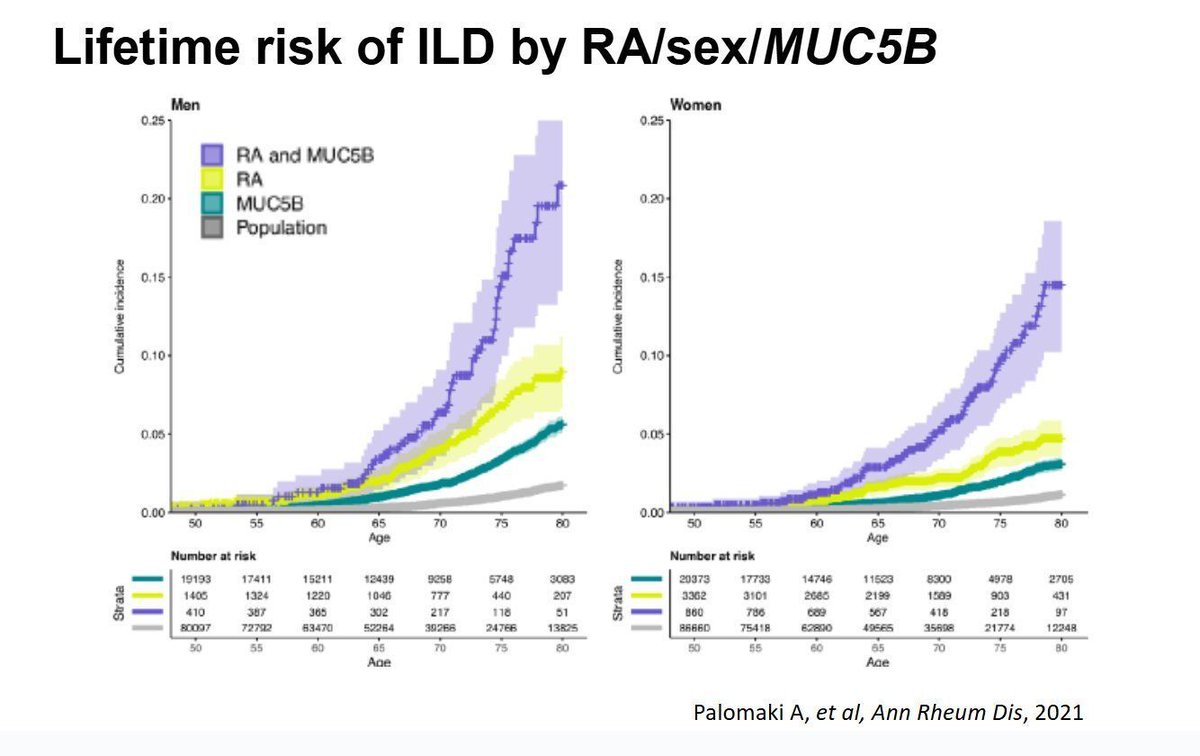
Lifetime risk of ILD by RA/sex/MUC5B status. We can see the synergistic effect. Also note RA>MUC5B in general. #RNL26 https://t.co/L5MOVVGIt3
Dr. John Cush RheumNow ( View Tweet)
RT @richardPAconway
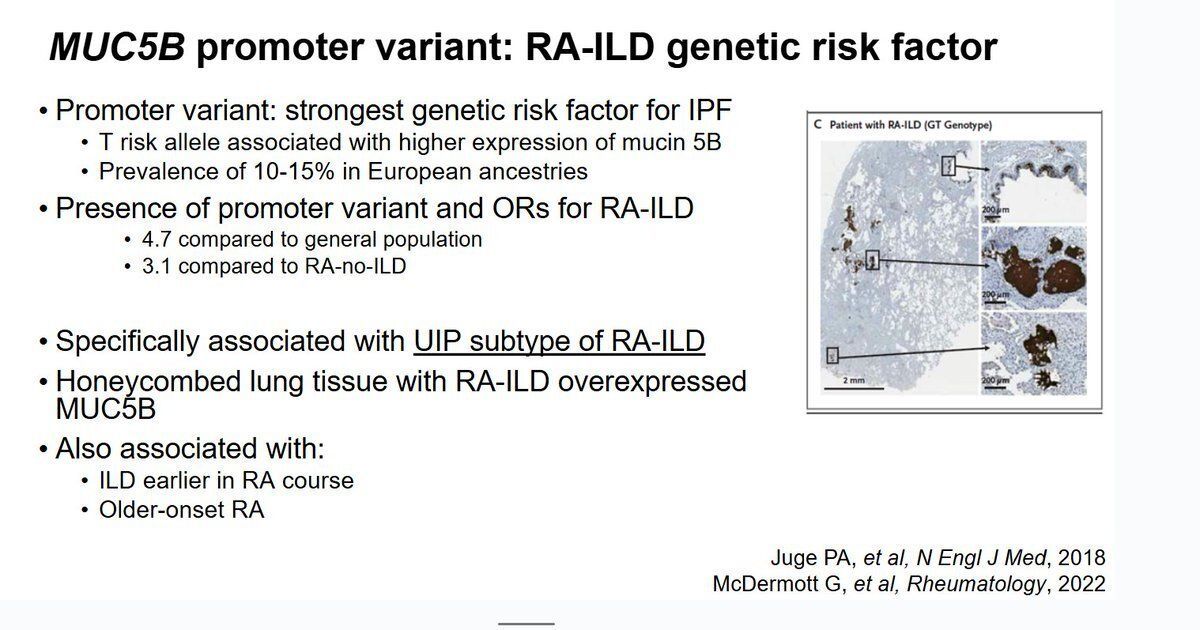
MUC5B is strong risk factor for RA-ILD. Specifically for UIP. Associated with both older-onset RA, and ILD earlier following RA presentation. #RNL26 https://t.co/qeLp1BqOEM
Dr. John Cush RheumNow ( View Tweet)

RT @ericdeinmd
RA-ILD #RNL26
Jeff Sparks
MTX and ILD
- Rare MTX-induced pneumonitis. 7 cases in n=4786 (0.3% cases) vs <0.1 on PBO, rare diff from ILD
- No increase in incident ILD - meta-analysis of 7 studies show OR 0.49 https://t.co/k2XeAzBsYB
Dr. John Cush RheumNow ( View Tweet)

RT @ericdeinmd
#RNL26 RA-ILD Jeff Sparks
ILD pooled prevalence 0.11
Sparks: "prevalence is high but not so high that we don't screen everyone," means lots of subclinical ILD
Subtypes:
UIP 50-60%, fibrotic
NSIP 30-40%, inflammatory
Less common: LIP, DIP, RB-ILD, DAD
Dr. John Cush RheumNow ( View Tweet)
RT @Gibson_RheumPAC
Obesity doesn’t just increase risk of rheumatic diseases-it worsens outcomes.
Patients with obesity have higher disease activity, poorer biologic response, and 20–25% lower remission rates in inflammatory arthritis. #RNL26
Dr. John Cush RheumNow ( View Tweet)

