Infiltrating macrophages expressing IL-6 and GM-CSF may drive the subacromial bursitis often seen in polymyalgia rheumatica, according to new research (abstract OP0015) prese

All News
Article
Article
Translating targeted therapy from bench to bedside has been more problematic in SLE than other autoimmune diseases, with many theoretically well-founded agents appearing to have failed in clinical trials as a result of inefficacy, problem with trial design and/or safety issues.
Janet Pope
Tweet
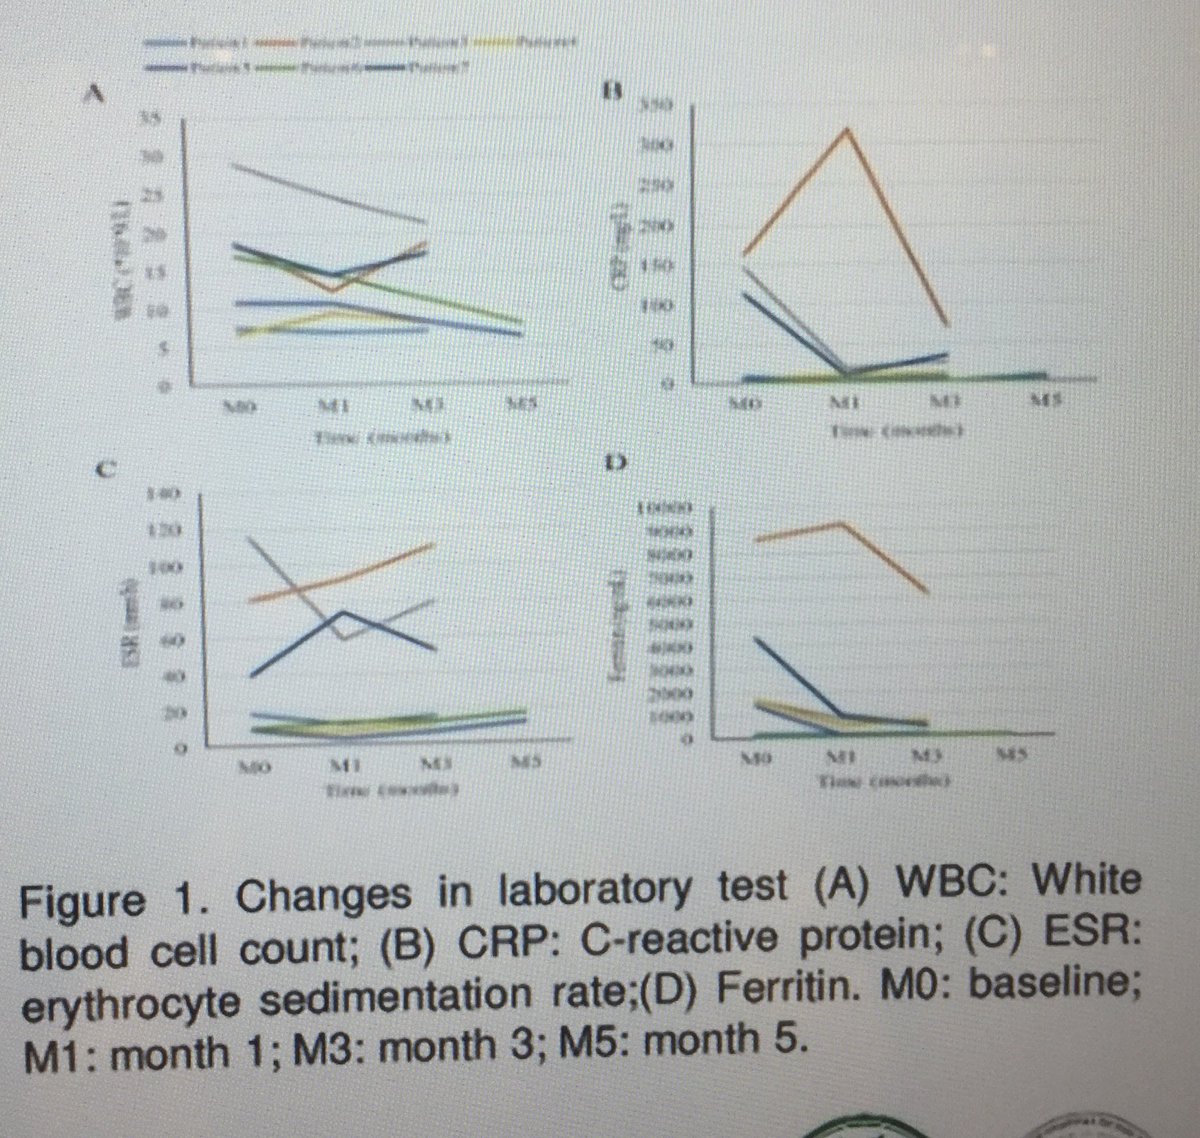
JAK will quiet Still’s disease? 7 w Still’s 4 refractory disease had benefit w #JAKi POS0014. Needs more data but looks promising most w partial response . 5 on #Tofacitinib and 2 w #Baricitinib. @eular_org #EULAR2022 POS0014 @RheumNow https://t.co/j9IRgT9XJf
Aurelie Najm
Tweet
Insightful session with H Schulze-Koops: JAKi-Are all promises fulfilled?
"JAKi have not shown us sufficient data to prove that they can induce remission or inhibit disease progression"
@RheumNow #EULAR2022 https://t.co/SKKAS1ViIU
Richard Conway
Tweet
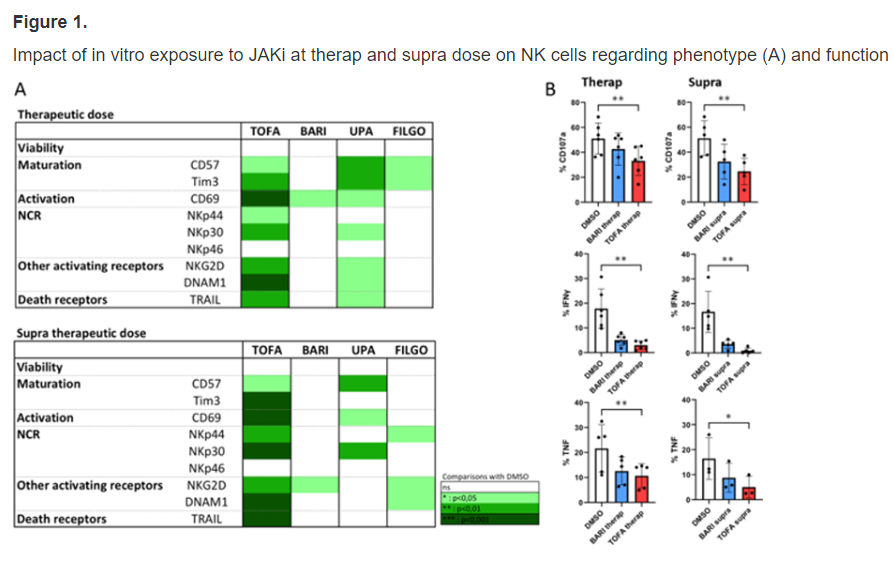
Meudec et al. Comparative effects of JAKi on NK cell function on cancer cells (lymphoma and lung cancer). Tofacitinib had most negative impact. Interesting given blanket black box based on tofa data! @RheumNow #EULAR2022 OP0265 https://t.co/XSE7hP60Ui https://t.co/MjtAJcvWAD
Richard Conway
Tweet
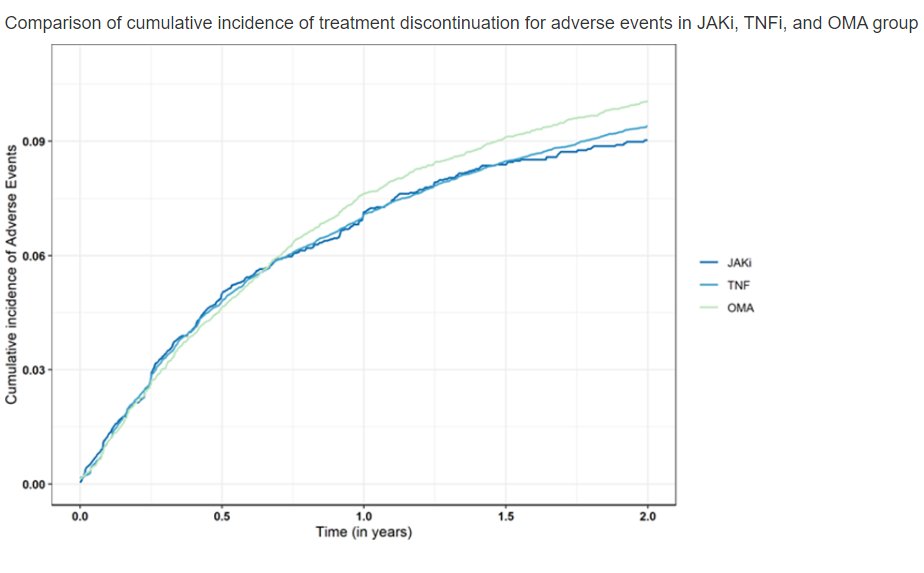
Nyam et al. JAK-pot study. >90000 treatment courses. No difference in aHR for treatment stop due to adverse events in JAKi vs TNFi or non-TNF bDMARD. @RheumNow #EULAR2022 OP0266 https://t.co/3tgADvH1Bq https://t.co/2qLRzfMB9c
Richard Conway
Tweet
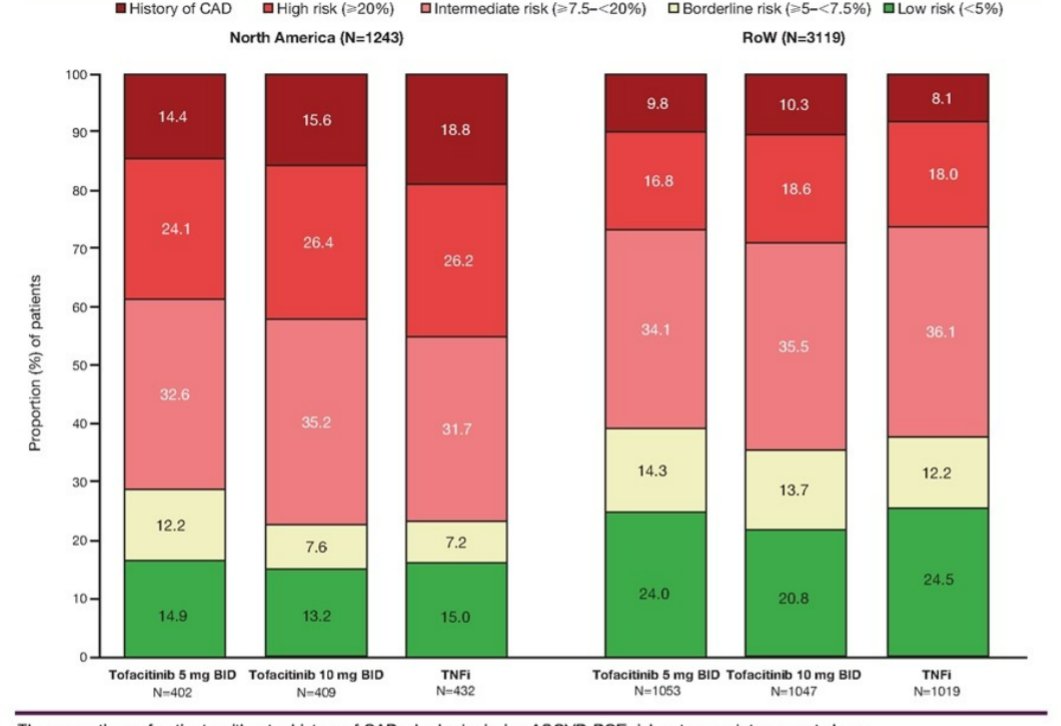
Szekanecz et al. ORAL Surveillance. Geographic differences in MACE largely driven by history CVD and high baseline risk in North America and ROW. @RheumNow #EULAR2022 POS0110 https://t.co/cR6a7N2KP5
Richard Conway
Tweet
Dougados et al. MACE in tofa clinical programme. Baseline CV risk important. Overall MACE IR 0.38 [0.26-0.54]. MACE IR lower than in ORAL Surveillance in CV enriched pop 0.72 [0.46-1.09]. @RheumNow #EULAR2022 OP0264 https://t.co/lGTTEx0X5p https://t.co/MvD6kjkpse
Aurelie Najm
Tweet
🧫 JAKi and NK
cells activation:
JAKi and particularly TOFA impacts NK cells:
*phenotype
*function
*impairs the control of proliferation of lung cancer and lymphoma cell lines
An explanation for the increase of cancer events in ORAL surveillance?
@RheumNow #EULAR2022 OP0265 https://t.co/LzMLdzcsDU
Janet Pope
Tweet
MACE events no diff in German RA Rabbit registry of only humans shows #baricitinib and #tofacitinib vs #TNFis @RheumNow @eular_org #EULAR2022 OP0135 https://t.co/O8iOA7jpal
David Liew
Tweet
Was ORAL Surveillance really a surprise?
Let's look post-hoc at all the other tofacitinib RCTs (ph 1-3b/4 +LTE)
Cardiovascular risk-enriched pts were always in the same MACE ballpark with tofa
ORAL Surveillance was worse, but clues were always there
OP0264 #EULAR2022 @RheumNow https://t.co/rB5SwVX2oc
Richard Conway
Tweet
Montastruc et al. VigiBase study of CV and VTE events in JAKi vs TNFi. >270000 events. DECREASE in MACE ROR=0.87 [95%CI 0.80-0.95]. INCREASE in DVT: ROR=3.99 [3.15-5.04], PE: ROR=3.47 [2.90-4.13] @RheumNow #EULAR2022 OP0268 https://t.co/lUin7ciXWt https://t.co/Gr4Kvd8F7R
David Liew
Tweet
MACE in JAKi vs TNFi: did spontaneous reporting pharmacovigilance pick it?
Vigibase: MACE (really MI) & VTE signals there before the scare
Always chance regulatory warnings cause stimulated reporting
but signal here was clear before RCT-driven alerts
OP0268 #EULAR2022 @RheumNow https://t.co/hTJD1gMgyy
Video: Further Considerations of the ORAL Surveillance Study
Further Considerations of ORAL Surveillance Study - this week there are new analyses and sub-analyses that further explain findings and who this data applies to. #EULAR2022
https://t.co/a2XKthtMbs https://t.co/kYNS1AesHT
Are TYK2 inhibitors ‘ticked’ to be part of the JAK family?
Are Tyk2 inhibitors JAK inhibitors?
Yes, no, maybe
Check out all of Dr. Janet Pope’s TYK2 Q&A.
https://t.co/IqeGqt6M4t https://t.co/kjWLVKVFP7
GM-CSF increased in patients with active ankylosing spondylitis, correlates with disease activity, not duration. TNFi does not affect GM-CSF levels. Could explain efficacy of JAKinibs and response for residual inflammation during TNF blockade.
@RheumNow #EULAR2022 ABST#OP0107
JAKi for nonradiographic axSpA
One area of continued interest for many rheumatologists is the field of non-radiographic axial spondyloarthritis. And the question of the utility of JAK inhibitors for the treatment of axSpA has been on the rise.
https://t.co/xq8ICyKKv0 https://t.co/o2iUgyU60A
Eric Dein
Tweet
#EULAR2022 ASAS/EULAR AxSpA Recs
⭐️Last: 2016
▶️All: education, exercise, 🚭
▶️❌csDMARD for axial disease
▶️TNF/IL17 (or JAK) with high disease: ASDAS>/=2.1
▶️Monoclonal TNF for uveitis/IBD, high PsO: IL-17
▶️Sustained remission: tapering of bDMARD "can be considered"
@RheumNow https://t.co/3yYU0Vb37r
Richard Conway
Tweet
RABBIT registry data on CV events with JAKi. Incidence rate low 0.41/100PY. No increase compared to TNFi RR 0.94 (0.39-2.38). No increase in high-risk group RR 0.90 (0.37-2.17). Reassuring with wide CI's. @RheumNow #EULAR2022 OP0135 https://t.co/vBSsnfeBoR https://t.co/iYDZsNwMye
Eric Dein
Tweet
#EULAR2022 OP0135:
German RABBIT 🐇 Registry:
⭐️ Observational, 46% Tofa, 54% Bari
No increased rate of CVD in JAK vs TNF inhibitor
🚨Unlike the ORAL Surveillance
@RheumNow https://t.co/O4IXg22Ybc