Januse kinase (JAK) inhibitors are targeted synthetic disease modifying anti-rheumatic drugs (tsDMARDs) that have risen in popularity as earlier treatment options for rheumatoid arthritis.

All News
Article
Article
Still's disease is an autoinflammatory disease characterized by spiking fever, rash, polyarthralgia, sore throat and even life-threatening complications, such as macrophage activation syndrome. It was first described by George Still in the late 1800s.
Does #baricitinib affect #fatigue in RA patients?
👉🏼Results from RA-BEAM and RA-BEACON
👉🏼4mg baricitinib significantly reduced fatigue, starting week 16, compared to placebo
👉🏼Effect independent of disease activity in active RA
Abs#1235 #ACR21 @RheumNow
https://t.co/0SKhUKJHd7 https://t.co/R76wc56u6I
FDA Update session: Proven Benefit of Baricitinib in Hospitalized COVID-19 from the ACT2 and COV-BARRIER Studies, showing it does not need to be given with Remdesivir (4 mg qd maz 14days) #ACR21 https://t.co/r6crPtu3ZH
#RA pts on #baricitinib less likely to discontinue treatment & more likely to achieve remission than pts receiving biologic /other tsDMARD.
👉🏼Results from RA-BE-REAL observational study
👉🏼Bari(2 or 4mg) vs biologic/other tsDMARD
Abs#1223 #ACR21 @RheumNow
https://t.co/WRN1OCX9Bq https://t.co/UCFF6hAY7G
Richard Conway
Tweet
Effect of BMI on PRO treatment response in PsA. Increasing BMI associated with lower response. More pronounced in TNFi than IL-17 or JAKi. Abstr#1327 #ACR21 @RheumNow https://t.co/qhgVlW72uM
Wk 12 disease activity predicts wk 24/26 remission/low disease activity with #upadacitinib 15mg in MTX-naïve or inadequate responders to MTX and/or TNFi pts.
≥50% improvement in SJC/TJC at Wk 12 was assoc with wk 24/26 remission/low disease activity.
Abs#1237 #ACR21 @RheumNow https://t.co/PAaCe5MAcu
David Liew
Tweet
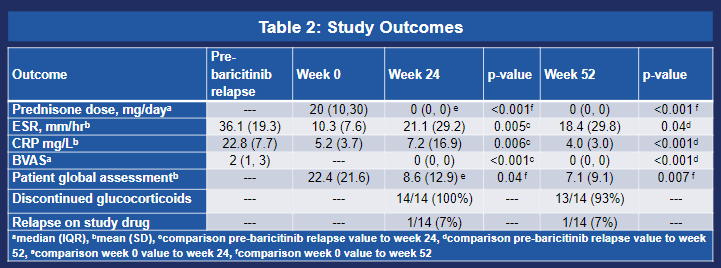
Baricitinib for *relapsing* GCA (Th1+Th17)
w abbreviated steroid wean (15-22w)
Despite being tougher to treat:
100% off steroids at 24w
93% off steroids at 52w
no ischemic Sx
promising as another GCA Rx option!
(post-cessation 4pts flared)
@MayoClinic #ACR21 ABST1396 @RheumNow https://t.co/dqFnHQYogk
David Liew
Tweet
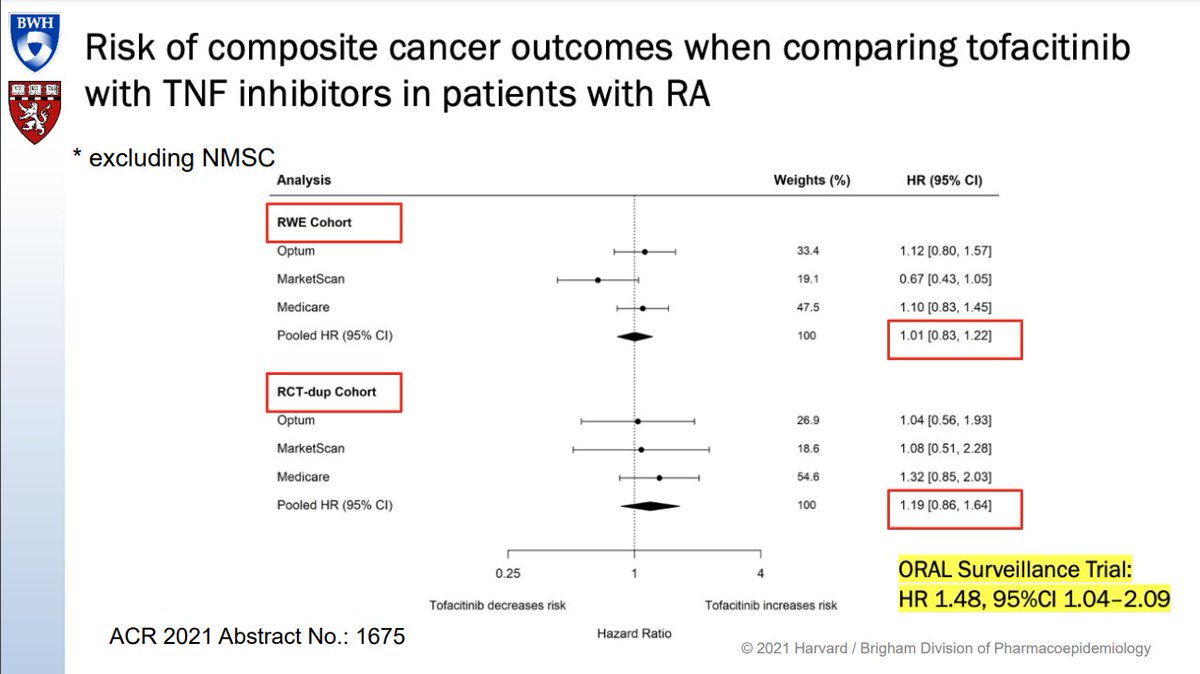
This feels like an excellent starting point for Tuesday's ORAL Surveillance malignancy discussion.
RWE Cohort: HR 1.01 (0.83-1.22)
RCT-dup Cohort: HR 1.19 (0.86-1.64)
ORAL Surveillance: HR 1.48 (1.04-2.09)
Interesting day 4 ahead!
great talk @SeoyoungCKim #ACR21 7S413 @RheumNow https://t.co/YSau21goMr
Akhil Sood MD
Tweet
Abstr 0983 mRNA SARS-CoV-2 Vaccine in RA Patients
Rubbert-Roth and colleagues found:
- RA patients developed anti-S1 antibodies slower and lower compared to controls
- Reduced titers among Abatacept & JAKi users
#ACR21 @RheumNow https://t.co/sXW8d53O8m
Aurelie Najm
Tweet
TOFA Post hoc analysis on 2000pts:
⬆️ Paraoxonase PON1 activity associated w/
⬇ risk of malignancies (not NMSC) in RA pts treated w/ TOFA, Adj on RA duration, age, and smoking.
A promising biomarker! #Abst980 @RheumNow #ACR21 https://t.co/fOILnAyDN9
Eric Dein
Tweet
#ACR21 Abst#0588. TNF vs non-TNFi in obese RA pts
⭐️TNFi use ⬆️ disease activity vs ABA in obese pts
⭐️TNFi use ⬆️ activity vs TCZ in non-obese pts
⭐️No diff w RTX, Tofa
▶️Further research needed: Wt-based dosing? SC vs IV?
https://t.co/K8WycPTgxW @Rheumnow #ACRBest
David Liew
Tweet
ORAL Surveillance MACE conclusions:
So this is fair: tofacitinib acts as a CV risk factor, there are many others, we need to address CV risk in RA pts.
Nevertheless, in terms of MI risk, tofa vs TNFi, if I had one CV risk factor, I know what I'd do.
#ACR21 ABST0958 @RheumNow https://t.co/4Z79XtTzl9
SELECT-AXIS 1: UPA 15 mg QD consistently efficacious over 2 years for ASAS40. Low radiographic progression rates in AS pts. No new safety findings were observed. Abs 0924 #ACR21 #RheumNow @RheumNow https://t.co/CWvH1OPGyR https://t.co/uC67fJZDCE
Dr. Antoni Chan
Tweet
With Deucravacitinib, a TYK2 inhibitor vs placebo, PsAID-12 and PsAID-9 scores were significantly improved
versus baseline at Week 16
and other PROs showing a clear improvement in PsA-related impact @RheumNow #ACR21 Abst#0750 https://t.co/JbeSE2dO94 https://t.co/pH79dXCYSs
David Liew
Tweet
Let's look at MI first.
Well, the numbers don't look great for tofa here.
fatal MI very small numbers
non-fatal MI - well that doesn't look good
(do we have combined both tofa doses vs TNFi?)
HR > 2 seems less than ideal - this would represent a substantial RF
#ACR21 @RheumNow https://t.co/5HSXFrMJCu
ORAL Surveillance: MACE events higher in TOFA vs TNFi. Independent risk factors: smoking, aspirin use, age ≥ 65 yrs, and male sex; TOFA vs TNFi tx in these pts assoc'd w/ numerically higher MACE incidence. Plenary Abs 0958 #ACR21 #ACRbest @RheumNow https://t.co/44af1KujqP
The Lancet Rheumatology
Tweet
Tofacitinib vs TNF inhibitors in #RA patients +50yrs with >1 CV risk factor; the data from ORAL Surveillance that we have all been waiting for! #ACR21
Risk of MACE related largely to baseline CV risk https://t.co/SpuKTtP8ql
ORAL-Surveillance, an open label Phase 3b/4 RCT of tofacitinib (JAKi) vs TNFi in RA
Numerical elevations in MACE and MI, highest among pts w/hx of CAD or high 10-year risk for MACE
I have been considering baseline CVD / VTE / CA risk when prescribing these since this broke https://t.co/8DAx8IgnZM