

A new treatment for AxSpA that has come on the scene are JAK inhibitors. In clinic, considerations for JAKi use are body mass index, smoking status, prior use of biologics and patients with high inflammatory states such as high CRP and inflammatory change on MRI scan of the spine and sacroiliac joints. There are further studies at #ACR22 which help answer these questions.

A Japanese large scale claims data study was able to collect 5-year data to study the treatment patterns in Still’s. In May 2019, intravenous tocilizumab was approved in Japan for Still’s disease. The study was designed to see patterns of steroid exposure before and after the approval of this therapy.

Eric Dein ericdeinmd
3 years 10 months ago
Let’s do this #ACR22
@RheumNow #rheumpix https://t.co/zTx4TynK44


Dr. John Cush RheumNow
3 years 10 months ago
AS, Lupus and Subclinical RA: What I'm looking forward to at #ACR22
There are three areas that always draw my attention each conference and this time is no different...
https://t.co/1h7NRgcqCm https://t.co/9P1UwrmjxW


Type I interferon (IFN) is a powerful immune activator that is present at high levels in the majority of patients with lupus, an autoimmune disease.
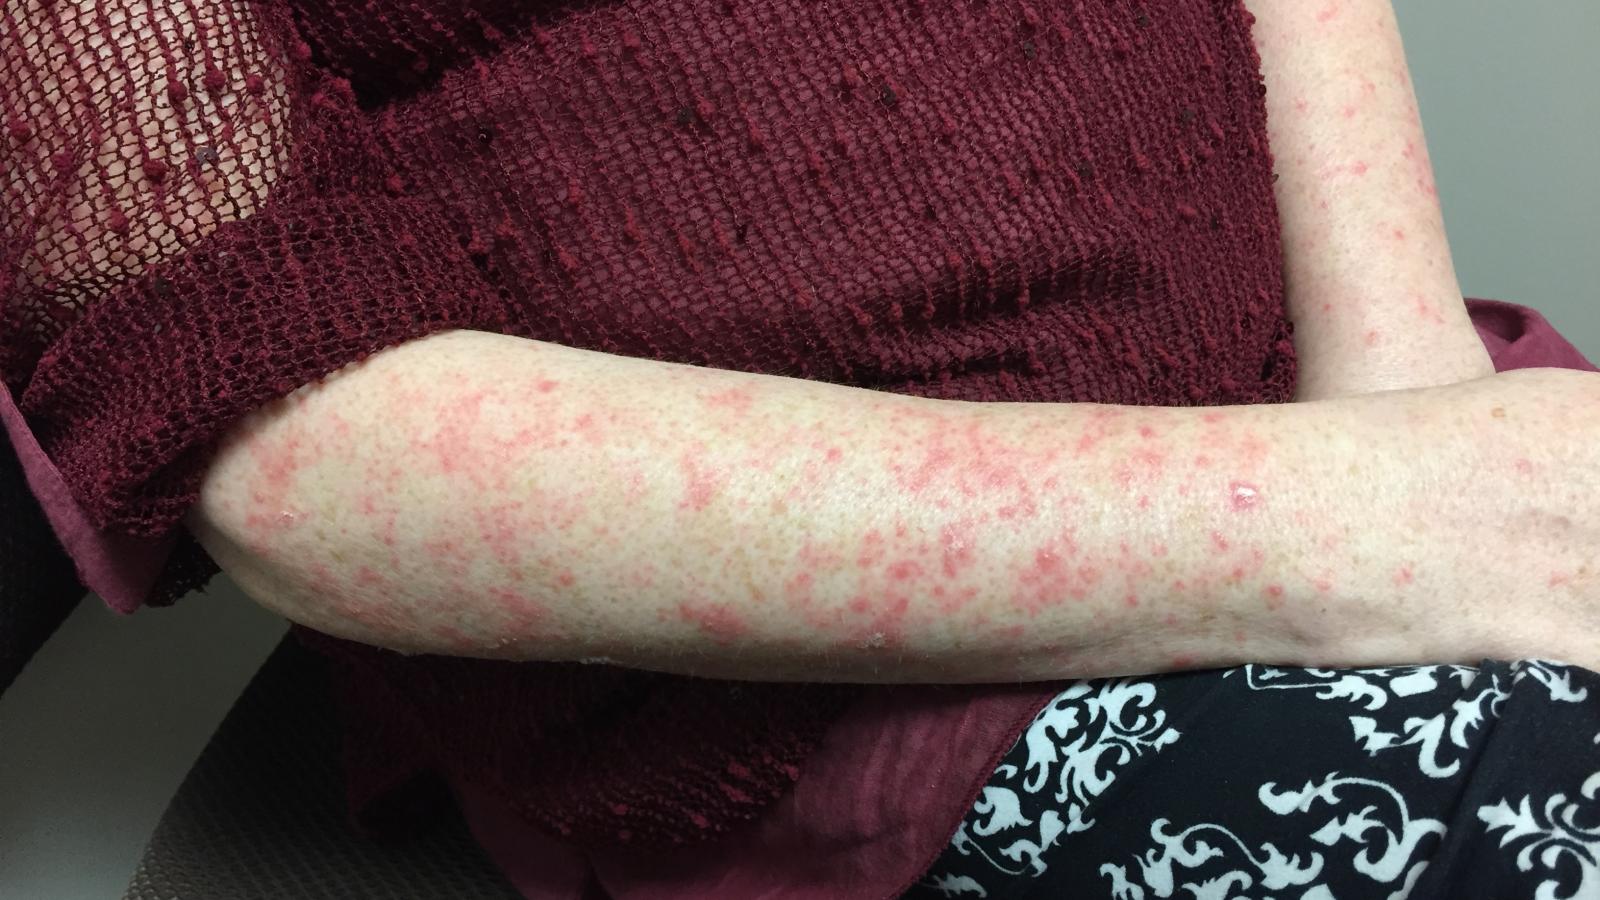
Despite a wealth of treatment options, a number of notable unmet needs remain in PsA, most notably the significant diagnostic delay that many patients endure. We are all aware that those with psoriatic skin disease are the most at risk cohort for PsA. Identifying patients with psoriasis who have, or are at increased risk of PsA, appears to be the low hanging fruit that we just can’t fully seem to grasp.
The COVID-19 pandemic has had a significant impact worldwide particularly among those who are immunocompromised. Numerous studies have highlighted the increased risk of acute SARS-CoV-2 infection among patients with rheumatic diseases (RD). Public health measures including masking, social distancing, and vaccination have helped to lower the risk of acute SARS-CoV-2 infection in this population.

Dr. Antoni Chan synovialjoints
3 years 10 months ago
Progression from non-radiographic to radiographic AxSpA is not the norm
● 16% progress over 5 years, 10-25% over 10 years
● Syndesmophytes in 20% over 4 years
● Male, MRI+ at baseline, response to NSAIDs are predictors of progression
Jose U Scher, Review @RheumNow #ACR22 https://t.co/FatodINTfn

Dr. Antoni Chan synovialjoints
3 years 10 months ago
ASAS-EULAR Rec for AxSpA 2022
◦ NSAIDs are first line
◦ b/tsDMARDs when ASDAS >2.1
◦ Uveitis/IBD ➤TNFi
◦ Psoriasis ➤IL-17i
◦ Review Dx if Rx failure
◦ Switch if active disease confirmed
◦ Taper bDMARDs if sustained remission
Jose Scher #ReviewCourse @RheumNow #ACR22 https://t.co/8fGwlZWBDS

Dr. Antoni Chan synovialjoints
3 years 10 months ago
IL-17i Ixekizumab (IXE) continuation superior to withdrawal in preventing relapse in PsA
● Withdrawal resulted in relapse at median 22 wk
● Continuation vs withdrawal 38% vs 85% relapse
● 96% regained control after reinstating IXE
Jose Scher #ReviewCourse @RheumNow #ACR22 https://t.co/TgIRe14Vud

Dr. Antoni Chan synovialjoints
3 years 10 months ago
Think of paraneoplastic presentations for
◦ RS3PE 16-30% malignancy
◦ PPP 12% pancreatic ca
◦ HPOA 1% lung ca
◦ EF 10% haem ca
◦ LCV 4% malignancy
◦ Erythromelalgia 10% haem ca
Screen for malignancies esp if treatment resistant
Capelli L #ReviewCourse @RheumNow #ACR22 https://t.co/tEaf7wCAcj

Dr. Antoni Chan synovialjoints
3 years 10 months ago
Not all dry eyes and mouth is due to Sjogren’s syndrome (SS). Think of mimics including diabetes, HCV, HIV, sarcoidosis.
Equally, not all parotid enlargement is due to SS. Think of mimics including IgG4, sialodenosis #ReviewCourse @RheumNow #ACR22 https://t.co/zPwRRtdGjT


Dr. Rachel Tate uptoTate
3 years 10 months ago
The calm before the #ACR22 deluge! Let’s go learn! Follow https://t.co/nDsfMGdiq8 for our conference coverage! @RheumNow #rheumpix @doctorRBC @DrPetryna @KDAO2011 @RichardPAConway @ericdeinmd @EBRheum @gensler_MD @Janetbirdope and more! https://t.co/nTX48dWA4g

Dr. John Cush RheumNow
3 years 10 months ago
Join Dr. Jack Cush and Dr. Arthur Kavanaugh as they discuss, dissect and deliberate about data presented at the #ACR22 meeting in Philadelphia.
https://t.co/WGUYSUmFYz https://t.co/yGSROf5XU6

Dr. Antoni Chan synovialjoints
3 years 10 months ago
Methotrexate (MTX) works in early PsA. Confirms what we see in clinical practice
◦ Mean disease duration 0.6y
◦ bDMARD naive
◦ MTX monotherapy
➢ ACR20 50.7%
➢ ACR50 30.6%
➢ MDA 22.9%
Good to know, our trusted friend MTX works
Jose Scher #ReviewCourse @RheumNow #ACR22 https://t.co/ECyM4qtliG


