
Article
Dr Jack Cush comments on this week's journal articles, reviews and studies.

Search for Terms or Answers
Dr Jack Cush comments on this week's journal articles, reviews and studies.

QD Clinic - Lessons from the clinic. In this video: Patients stable on a biologic need guidance on when, and if, they can stop their biologic.

QD Clinic - Lessons from the clinic
Active HBV infection (HGsAg+) on anti-viral therapy but needs a biologic - what should you use?

The availability of biologic biosimilars has thus far had negligible impact on prescribing practices in the United States, in stark contrast to what has been observed in some European countries, researchers reported.
A controlled clinical trial has shown that giving the IL-6 receptor antibody, tocilizumab (TCZ), to patients with Takayasu arteritis (TAK) results in clinical efficacy and has a steroid sparing efffect.
NEJM has published the results of the TULIP2 trial with anifrolumab, an alpha interferon blocker, in the treatment of systemic lupus erythematosus, showing significant improvement (over placebo) in multiple lupus outcome measures, including BICLA, SRI-4, CLASI and others.
Statin-induced myositis, often with anti-HMGCR autoantibodies can be difficult to manage, Arthritis Research & Therapy yhas published the experience of 55 patient with HMGCR myopathy, demonstrating that while steroid management may be reasonable in select patients, the use of tr
Dr. Jack Cush reviews the news and journal reports from this past week on RheumNow.com. The podcast covers: best therapies for dactylitis and enthesitis; we have a new knockout for knee pain in OA; and are you on the naughty or nice list when it comes to the new ACR-AF guidelines for arthritis? This and more. Tune in.
Rheumatoid arthritis patients taking tofacitinib (Xeljanz) plus methotrexate who achieved low disease activity (LDA) may be able to withdraw from the latter agent without significant worsening of disease activity, a researcher reported at EULAR 2019 in Madrid.

It’s a great time to be a rheumatologist and to manage RA. But, if you keep doing what you’re doing, you’re going to keep getting what you’ve got.

In the United Kingdom, NICE has looked to the British Society of Rheumatology (BSR) to develop evidence based guidance on the safe use of biologic DMARDs in patients with inflammatory arthritis.

Two recent studies have examined the effect of starting abatacept upon the risk of serious hospitalized infections or cancer, showing divergent results from claims data analyses.
We have options that are endless – we have 28 biologics in rheumatology; 19 approved for RA in the last 20 years, but 15 of these are me-too copies or biosimilars. We currently have 2 JAK inhibitors and may have 3 or 4 by year end. But what we really need is the right drug, at the right time, in the right patient – but how will we know.
Current ACR and EULAR guidelines list TNF-inhibitors (TNFi) abatacept, rituximab, and tocilizumab as being equally effective after methotrexate or as second line therapies when treating rheumatoid arthritis.

The SEAM-PsA study examined the efficacy of methotrexate monotherapy, etanercept monotherapy or the combination of MTX and ETN in psoriatic arthritis patients, and found that ETN monotherapy was equivalent to combination therapy - and that both were superior to MTX alone in clinical (ACR and MDA) and radiographic responses.

The European Medicines Agency safety committee (PRAC) has concluded that Xeljanz (tofacitinib - TOFA) could increase the risk of blood clots in the lungs and in deep veins in patients who are already at high risk for venous thromboembolic events. The PRAC is recommending that TOFA should be used with caution in patients at high risk of blood clots (VTE), regardless of dose used.
The American College of Rheumatology (ACR), in partnership with the Spondylitis Association of America (SAA) and the Spondyloarthritis Research and Treatment Network (SPARTAN), released the 2019 Update of the Recommendations for the Treatment of Ankylosing Spondylitis (AS) and Nonradiographic Axi

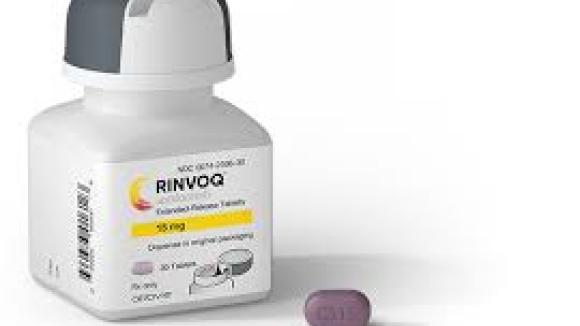
The US Food and Drug Administration (FDA) on Friday, August 16, approved AbbVie JAK1 inhibitor, Rinvoq (upadacitinib) for adults with rheumatoid arthritis with moderately to severely active disease either not responding to, or intolerant of, methotrexate (MTX).
By downloading this material, I acknowledge that it may be used only for personal use and personal education and that I will accredit RheumNow.com as the source and owner of this material. Commercial use or mass reproduction of this material without permission from RheumNow (info@rheumnow.com) is prohibited.
