Hitting the home stretch, day 3 presentations were big! Here are a few of my favorites: secukinumab efficacy in juvenile PsA; VEXAS - predicting poor outcomes; and the FDA Safety Update session.

All News
Article
Article
Should we start considering therapeutic drug monitoring when prescribing TNFi for treatment of our rheumatologic conditions?

Article
Psoriatic arthritis is currently experiencing a burgeoning selection of treatment options. While this is a very welcome development in a disease which has had less treatment options compared to RA, it leaves us with a difficult conundrum: which agent to choose for an individual patient.
Akhil Sood MD
Tweet
Abst 1517
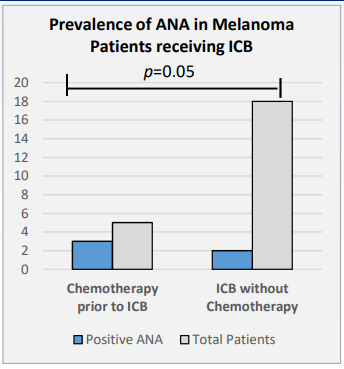
Weinmann & colleagues studied prevalence of autoantibodies in Melanoma pts treated w/ ICI & developed rheumatic IRAE
- Most common rheumatic IRAE = inflammatory arthritis
- Higher prevalence of ANA in those tx w/ chemo prior to ICI
#ACR21 @RheumNow https://t.co/7qgogSMjUr
Eric Dein
Tweet
#ACR21 Ab#1941: ORAL Surveillance VTE risk
▶️Tofa 10 BID risk > 5 BID > TNFi for VTE, DVT, PE
▶️Age, male, obesity, HTN, h/o VTE, oral contraception/HRT, steroids, antidepressants were risk factors
@RheumNow
https://t.co/JOKNyYVZfX https://t.co/mTkgkwPIT6
Eric Dein
Tweet
#ACR21 Ab#1939: Tofa CV Outcome (STAR-RA)
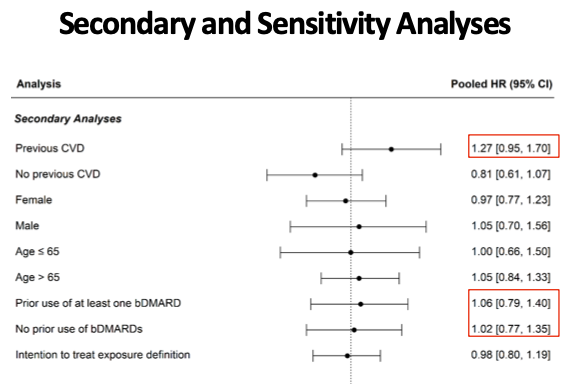
▶️Pooled data does not show ⬆️ risk of CVD
▶️Trend in pts w prior CVD -HR 1.27 (0.95-1.7), cannot r/o CVD risk in pts w risk factors
Less clear than oral surveillance data, but concerns in those w risks
https://t.co/JOKNyYVZfX @Rheumnow https://t.co/GGYJfxcqhc
Richard Conway
Tweet
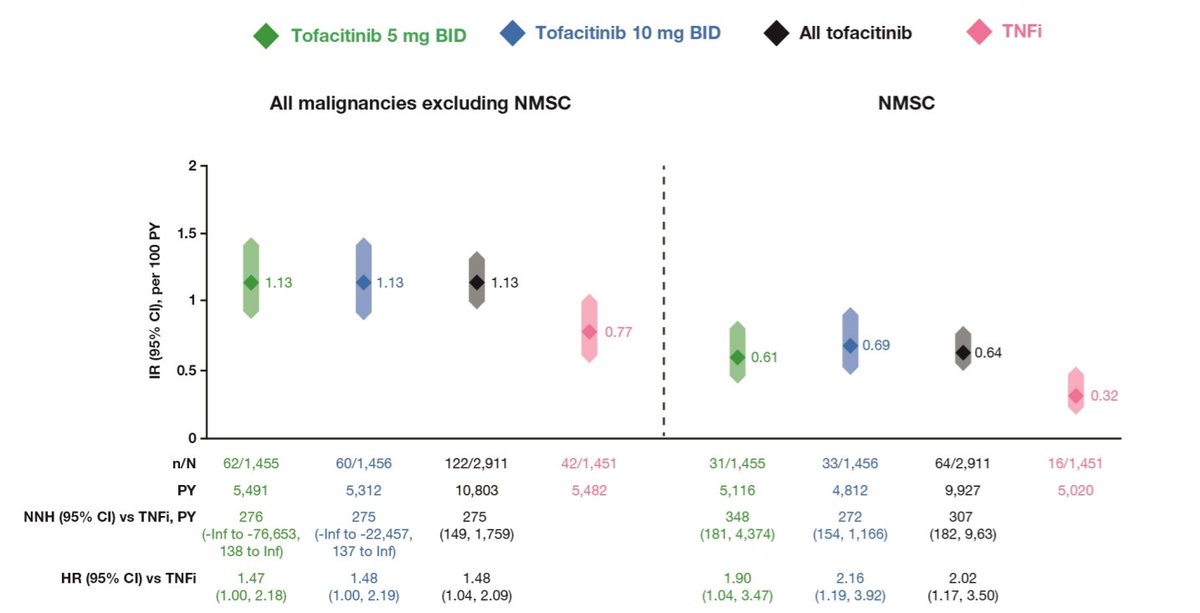
ORAL Surveillance malignancy risk @RADoctor . Numerically higher at both doses tofacitinib compared to TNFi . Abstr#1940 #ACR21 @RheumNow https://t.co/uc2k5EaiRq
David Liew
Tweet
STAR-RA, CV risk
large insurance datax3
tofa vs TNFi
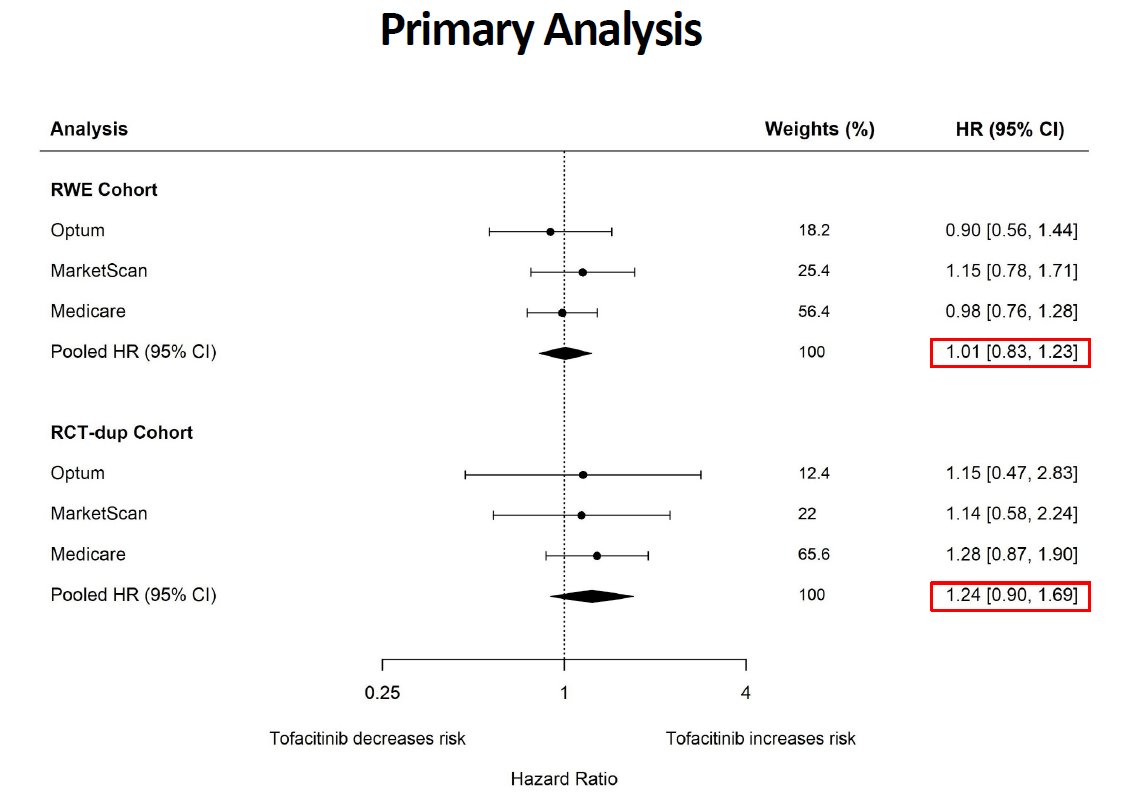
all comers: HR 1.01 (0.83-1.23)
one CV RF + any MTX: HR 1.24 (0.90-1.69)
prev CVD: HR 1.27 (0.95-1.70)
not sig
but surely okay to say baseline CV risk + tofa makes me a little nervous?
@SeoyoungCKim #ACR21 ABST1939 @RheumNow https://t.co/LmmL5zgv9u
Aurelie Najm
Tweet
Another study linking long term GC and CV risk in RA!
Medicare data >65yo 130000+ pts
1-year incidence CV ⬆️ as follows:
📍Dose ≤5mg 1.4%
📍Dose 5-10mg 1.7%
📍Dose >10mg 1.9%
Not replicated in younger pts (Optum data)
#ACR21 #Abst1915 @RheumNow https://t.co/DLXdfvfiBW
#ACR21 Abs#1915
👉🏼Chronic steroid use in older adults on stable DMARD therapy
assoc w/ ⬆️CV risk
👉🏼Risk even present among older adults receiving low dose ≤5mg/day
👉🏼Larger studies needed in younger healthier adults
@RheumNow https://t.co/Lsj5YBz7IG
Richard Conway
Tweet
Long-term low dose glucocorticoid use associated ⬆️cardiovascular risk. Clear effect in Medicare population (older), not evident in Optum (younger). Dose dependent. Abstr#1915 #ACR21 @RheumNow https://t.co/oFet3Hhsfo
Important late breaker @TerrierBen, DBRCT of RTX vs GC (FFS=0) or CYC (FFS>0) for EGPA
RTX not superior to CYC (64% RTX vs 60% CYC BVAS remission d180, p = 0.745); similar in subgroups
Feel like this lends support to (~surprising) ACR/VF recs for EGPA?
#ACR21 #ACRAmbassador https://t.co/gpsPtXF6pj
Janet Pope
Tweet
Why would higher active dose of #methotrexate with sc admin & more metabolites polyglutamates which can give side effects have LESS AEs? Never understood it! #ACR21 abst#1695 @RheumNow https://t.co/qrEKofX1cl
sheila
Tweet
Post hoc analysis of pooled data from 19 clin trials on SEC & CV risk & systemic #inflammation in PsO, PsA, AS
📌Traditional CV parameters remained stable on all SEC treated grps
📌SEC sig. ⬇hsCRP & NLR
@RheumNow #ACR21 abs1835 https://t.co/iCaGFbXNXn
David Liew
Tweet
b/tsDMARDs + tumor response in rheum irAEs
Excellent point by @CCalabreseDO @LCalabreseDO:
- despite progression in 5/10, DMARD contribution uncertain (bad cancer)
- without DMARD, ICI would have had to stop
crucial question, prospective study needed
#ACR21 ABST1519 @RheumNow https://t.co/omJnTNVscH
David Liew
Tweet
Autoantibodies are underrated in rheumatic irAEs (?B cells in general), but probably not your usual.
If Ab are of interest, suspect we're going to have to look at non-classical ones
Elegant from @NilashaGhosh @MPostow @got_rheum @lovetolearn27 #ACR21 ABST1520 ABST1521 @RheumNow https://t.co/tLSJOZw1YG
David Liew
Tweet
For patients with inflammatory irAEs, what's your preference of bDMARD/tsDMARD?
(keeping in mind both irAE response and tumor response)
#ACR21 irAE Study Group run by @CCalabreseDO @NAbdelwahabMD @ReidMDMPH
@RheumNow
Safety profile of #upadacitinib in #RA, #PsA, #AnkylosingSpondylitis
👉🏼AE rates similar across UPA, ADA & MTX in RA, and UPA & ADA in PsA
👉🏼No new safety risks with long-term use
👉🏼#Herpeszoster & incr CPK more common w/ UPA vs ADA/MTX
Abs#1691 #ACR21 @RheumNow https://t.co/tKYi65kB5r
Eric Dein
Tweet
#ACR21 Ab#1681: ATI-450- MK2 Inhibitor
⭐️Downstream MK2 mediated inflamm drive of p38.
⭐️Hope this would avoid tachyphylaxis in p38 inhibitor meds
▶️Phase2a study in 19 pts: Well-tolerated (SEs: UTI, ventricular extrasystole), good 12 week data
@Rheumnow https://t.co/6lo7zPJUpx
SELECT-EARLY results for #upadacitinib in #RA
👉🏼UPA better than MTX for clinical response and remission
👉🏼⬆️rates of HZ, neutropenia, CPK elevations
👉🏼No new safety risks identified
Abs#1692 #ACR21 @RheumNow
https://t.co/wJy7MK4pyF https://t.co/YNpE1Axiw0