

All News

Accdg to this retro analysis of their prospective cohort study from Toronto, 47 pts (10%) had D2M axSpA of whom 14 had tx-refractory dse.
D2M pts - longer symptom duration; ⬆️ASDAS, BASDAI, BASMI, BASFI & ⬆️CRP
💡Consider non-dse factors in D2M pts
#ACR25 @RheumNow Abs0547 https://t.co/MUUyyELbw8
sheila RHEUMarampa ( View Tweet)

#0191 We found that in a large South London RA cohort, use of advanced therapy in moderate disease (DAS28 3.2-5.1) generally followed NICE guidance. Gaps often reflected telehealth limiting DAS assessment and patient hesitancy. Self-assessment tools may help. @RheumNow #ACR25 https://t.co/UMGtkfABHn
Mrinalini Dey DrMiniDey ( View Tweet)

Real-world T2T strategy from MONITOR-PsA cohort:
🎯 At 48 weeks - 33.6% (49/146) of pts achieved PASDAS 'moderate' response & 37% (54/146) achieved a 'good' response
This was close to the T2T outcomes of the TICOPA trial
Adapt a T2T approach in PsA tx
#ACR25 @RheumNow Abs0572 https://t.co/FPiFIiO8Oe
Links:
sheila RHEUMarampa ( View Tweet)

SELECT-GCA (upadacitinib in GCA for 52w)
we hoped it might have ongoing effect post-cessation
Do we need to continue upa?
Extension data (second year) flare survival curves are clear:
continuing upa far outperforms placebo
It seems >2y toci/upa for GCA
#ACR25 ABST0776 @RheumNow https://t.co/uJA3uQyWxb
David Liew drdavidliew ( View Tweet)

Post-hoc PEXIVAS study, estimating risk of relapse from baseline variables
Lotsa fancy stats, mostly corroborated known risk factors, but model predicted relapse reasonably well!
Probably useful for approach to monitoring... mayyybe treatment?
#ACR25 @RheumNow #Abstr0722 https://t.co/XI9y8KgDNR
Links:
Mike Putman EBRheum ( View Tweet)

Mease et al. Sometimes perspective is all important! We worry about apremilast causing GI effects, anorexia, weight loss. Here we see reported benefits for weight loss and HbA1c. @RheumNow #ACR25 Abstr#581 https://t.co/CJjS0VZxWH
Richard Conway RichardPAConway ( View Tweet)

Tracking RA disease activity got a measurable boost in the VA: a 3-month multimodal rollout (feedback, EHR tools, just-in-time lists) raised DAM documentation up to 10%. Small structural changes, big data gains.
@RheumNow #ACR25 Abstract#0221
Jiha Lee JihaRheum ( View Tweet)
Why do some clinics excel at RA disease activity tracking while others struggle? In the VA, success came down to structure: RA-specific clinics, templates, and staff. Barriers? Time, missing labs, and workflow gaps.
@RheumNow #ACR25 Abstract#0222
Jiha Lee JihaRheum ( View Tweet)

Managing lupus is complex. How do we ensure quality care?
Abstract #0218 convened 8 focus groups:
✅ Support for patient navigators
⚠️ Barriers: low resources, staff turnover
💻 Solution: EHR outreach workflow to flag missed visits & labs
@RheumNow #ACR25 https://t.co/BWaIMMEPit
Akhil Sood MD, MS AkhilSoodMD ( View Tweet)
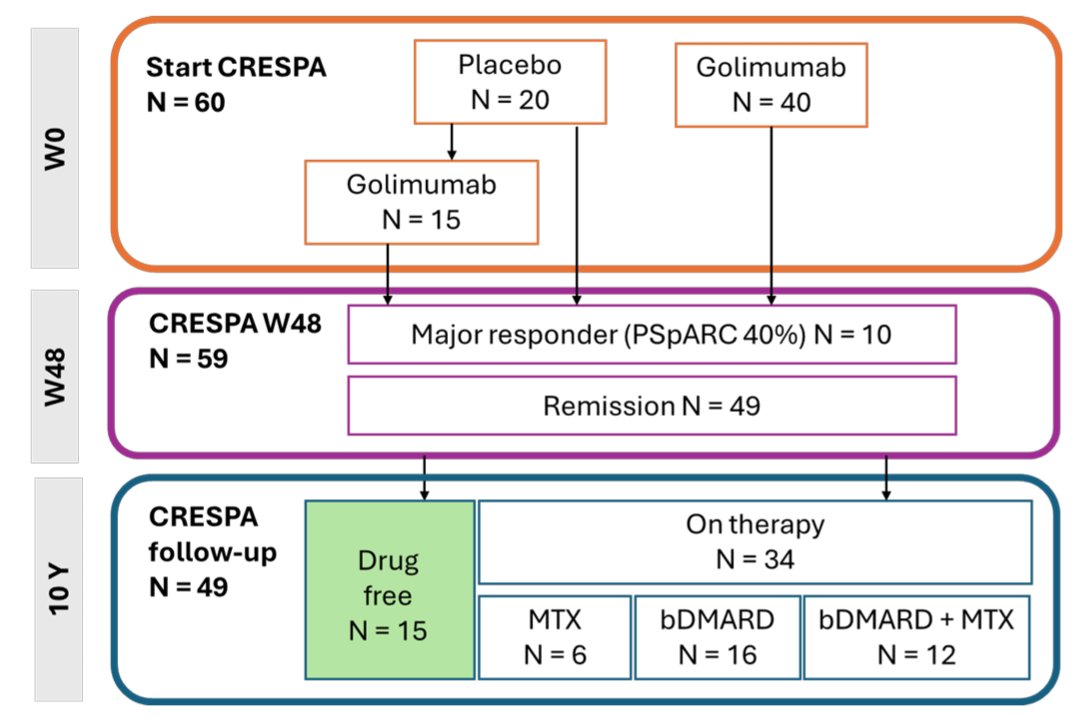
Damen et al. 10-year follow-up of CRESPA study. Treatment withdrawl trial in early peripheral SpA. 38% in drug free remission. 82% in remission. @RheumNow #ACR25 Abstr#568 https://t.co/KOVW5pSbJg
Richard Conway RichardPAConway ( View Tweet)
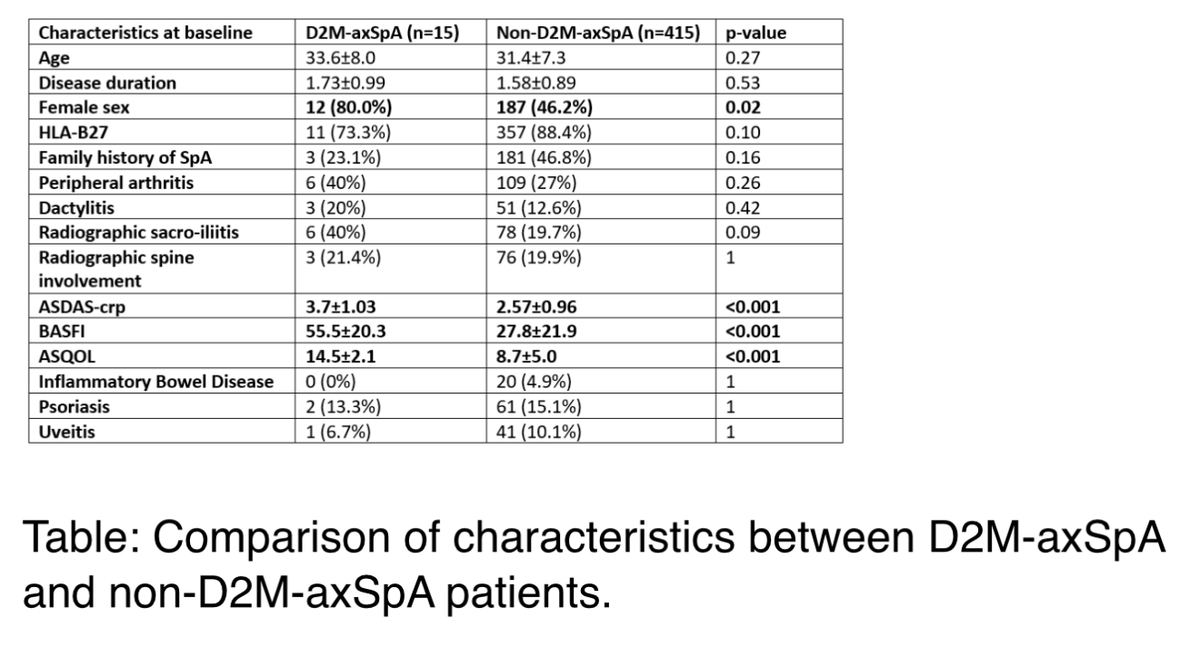
DESIR cohort of early axSpA:
✳️Factors assoc w/ D2M axSpA - female sex, ⬆️ASDAS-CRP ⬆️BASFI ⬆️ASQOL at baseline.
✳️ Low prevalence of pts meeting D2M definition (15 pts - 8.4% bDMARD-treated)
#ACR25 @RheumNow Abs0544 https://t.co/fBUh3myKcz
sheila RHEUMarampa ( View Tweet)
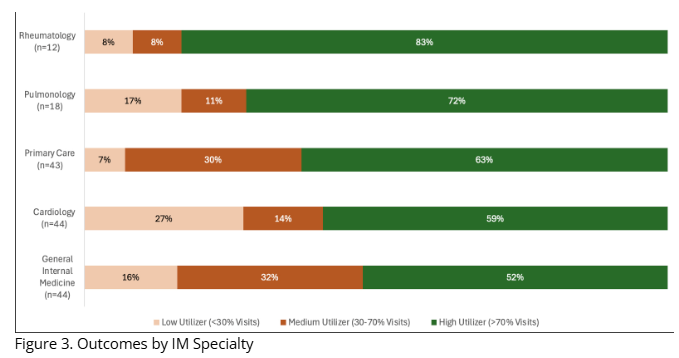
Abstract #0189: Rheumatologists are early adopters and high utilizers of #AI scribes.
📊 Adoption: 41%
🧑💻 Retention: 100%
💬 High utilizers (> 70% visits): 83%. The highest among IM subspecialties
🕒 AI scribes reduced EHR time across all measures.
@RheumNow #ACR25 https://t.co/TBurWUKhMl
Akhil Sood MD, MS AkhilSoodMD ( View Tweet)

This retrospective cohort analysis by Dr. Lihi Eder et al showed that among patients with PsA, those w/ high dse activity & high 3VAS scores were assoc w/⬆️ risk of atrial tachyarrythmias.
Main message: PsA conveys ⬆️CV risk; inflamm control is key!
#ACR25 @RheumNow Abs0522 https://t.co/7sRM7K4V1c
sheila RHEUMarampa ( View Tweet)

Come to our first #HealthLiteracy poster of #ACR25!
#0190
Cluster analysis >900 people with IA
Lowest health literacy cluster assoc w:
4× ⬆️anxiety/depression
2× ⬆️disease activity, vs highest HL
Higher HL assoc w older age & ⬆️comorbidities but fewer mental health Sx
@RheumNow https://t.co/iIRXaOl4qZ
Links:
Mrinalini Dey DrMiniDey ( View Tweet)

How does cMRI change over time in cardiac EGPA?
Cheng et al. retrospectively reviewed:
- 11 EGPA pt with LGE on initial cMRI
Despite treatment:
- 10/11 persistent LGE on 2nd cMRI
- 4/4 on 3rd
- 2/2 on 4th
Unclear use as a monitor of tx response
@RheumNow #ACR25
Brian Jaros, MD Dr_Brian_MD ( View Tweet)

#ACR25 Abstr#0772. Should we be worried of #SLE patients with low uPCR 0.25-0.49? Kidney biopsy in N=28 + poor prognostic (Non-White, active serology or active sediment)
- 71% had LN (No class IV or Mixed)
- 46% actionable LN
Cost-effectiveness data needed.
#ACRBest @RheumNow https://t.co/Bt3fuA3aJh
Links:
Md Yuzaiful Md Yusof Yuz6Yusof ( View Tweet)

AI-enhanced MRI integrating STIR and T1-weighted MRI with BME data reflecting both inflammatory and structural changes, enabling the AI model to predict clinical diagnoses of axSpA with accuracy of 82%. Successfully identified axSpA patients who did not meet the ASAS criteria for https://t.co/dLlGj0ZFpj
Antoni Chan MD (Prof) synovialjoints ( View Tweet)

Plenary session at #ACR25!
#0772 When should we biopsy in SLE?
In pts with uPCR 0.25-0.49 g/g + LN predictors, 69% already had LN (many Class III/V). Low C3/C4 were most important factors.
0.5 g/g cutoff may delay diagnosis and treatment. Time to rethink thresholds? @RheumNow
Mrinalini Dey DrMiniDey ( View Tweet)

Early, low level proteinuria is a harbinger in SLE. ~50% with elevated UPCR but <0.5 had actionable LN on early bx.
Risk factor = low c3/c4
Urine biomarkers promising
#ACRBest #ACR25 @RheumNow https://t.co/WuNPKeqeid
Links:
Brian Jaros, MD Dr_Brian_MD ( View Tweet)

From Dr. Petri at Plenary - even small amounts of proteinuria are a PROBLEM. Reduction of microalbuminuria by even 10% improves mortality! #ACR25 @RheumNow https://t.co/hjmH26vXIb
Brian Jaros, MD Dr_Brian_MD ( View Tweet)

