

Dr. Jack Cush reviews the news from the past week on RheumNow.com.

The current edition of Lancet Diabetes & Endocrinology suggests that neither vitamin D supplementation, nor dose, will improve bone density or prevent fractures in adults. (Citation source: https://buff.ly/2O9tqxI)

Use of wearable activity trackers was associated with increases in the number of daily steps among individuals with rheumatic and musculoskeletal disorders, a meta-analysis found.
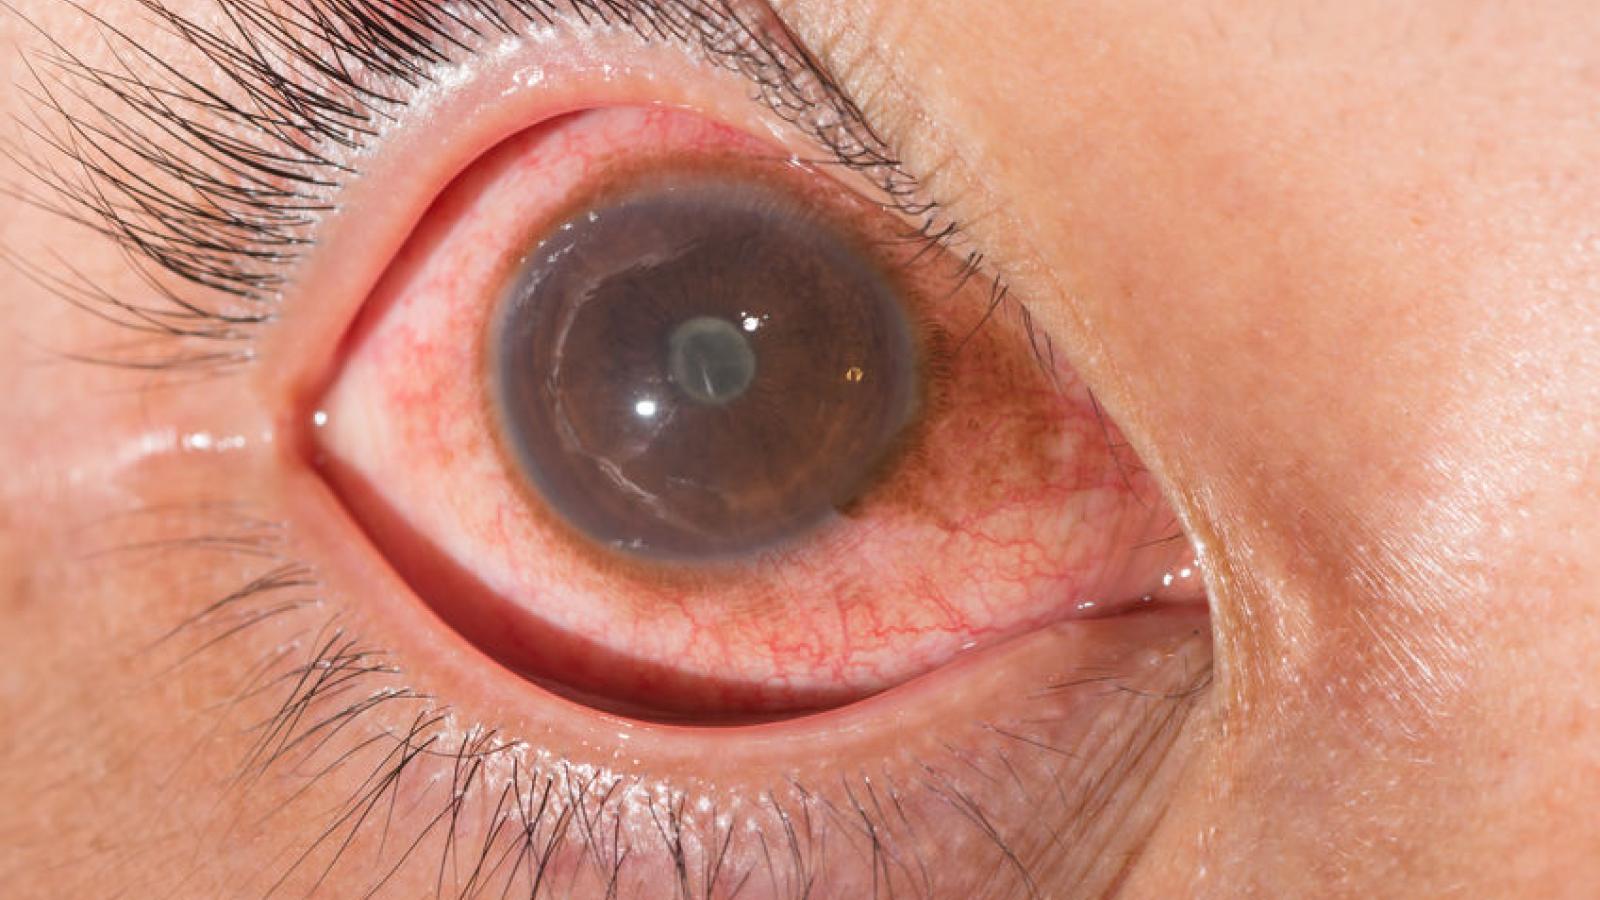
Researchers from Germany have studied a large cohort of juvenile idiopathic arthritis (JIA) patients and shown that JIA disease activity scores and laboratory biomarkers could be used to better define the group of JIA patients at high risk of uveitis onset.

The NEJM reports that zolendronic acid was shown to significantly lower the risk of nonvertebral or vertebral fragility fractures in older women with osteopenia.
The Norwegian connective tissue disease (CTD) and systemic vasculitis (PSV) registry (NOSVAR) studied patient outcomes over a 15 year period and found overall mortality to be higher in the CTD compared to the PSV group.
Multiple studies have shown that elderly rheumatoid arthritis (RA) patients tend to be under-treated and receive DMARD therapies less often than younger RA patients. Now a VAMC study shows that the elderly are less likely to receive biologic agents yet are as likely to be subjected to glucocorticoid use.
Males and females can both be affected by axial spondyloarthritis (axSpA). A recent study shows that while there are some differences and similarities, HLA-B27 and imaging are still pivotal elements for diagnosis of axSpA in both genders.

Only inhibitors of IL-1 (canakinumab) and IL-6 (tocilizumab) are FDA approved for use in children with systemic onset juvenile idiopathic arthritis (sJIA). Now, long-term data from the extension studies from two phase III studies shows that canakinumab yields long-term improvements with reduced glucocorticoid dosing with no new safety findings with long-term use.
Researchers from the British Society for Rheumatology Biologics (BSRBR) set out to define under what circumstances will rheumatoid arthritis (RA) patients manifest biologic disease-modifying antirheumatic drugs (bDMARDs) refractory disease.
Using the patients from the BSRBR Register (2001 to 2014) they defined patients as bDMARD refractory when they initiated their third class of bDMARD.

