
Article
NSAIDs have been linked to an increased risk of cardiovascular disease, but does this also hold for osteoarthritis (OA) patients.

Search for Terms or Answers
NSAIDs have been linked to an increased risk of cardiovascular disease, but does this also hold for osteoarthritis (OA) patients.

Dr. Jack Cush reviews the news and journal reports from the past week on RheumNow.com, including new SLE criteria, ULT in gout and MSU reductions, IVIG in ANCA vasculitis and non-TNF biologics outperform the TNF inhibitors.

A NEJM report shows that the use of vitamin D3 supplementation (4000 IU per day) in those without diabetes or vitamin D deficiency failed to significantly lower risk of type 2 diabetes (compared to placebo).

A single-center cohort analysis shows that lung disease is increasingly seen in children with systemic juvenile idiopathic arthritis (SJIA), especially those complicated by macrophage activation syndrome.
Prior to 2013, reports of pulmonary disease in SJIA were rare, but since there have been increasing reports of alveolar hypertension, interstitial lung disease and pulmonary alveolar proteinosis; often with a high mortality rate.
As such, since 2014, the Cincinnati Children’s Hospital Medical Center has seen an increase in lung disease and severe lung disease in SJIA.
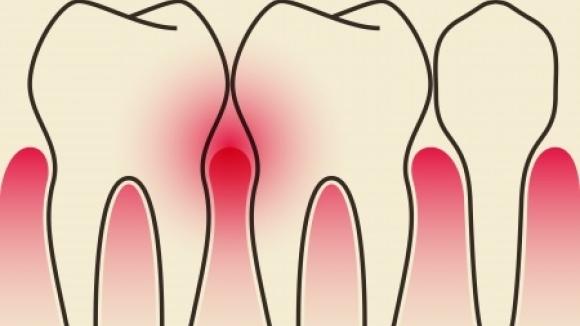
A cross-sectional study 48 CCP–positive "at risk" individuals (without arthritis) were shown to have an increased prevalence of periodontitis and P gingivalis when compared to 26 early RA (ERA) and 32 controls.
The European League Against Rheumatism (EULAR) and the American College of Rheumatology (ACR) have jointly developed new classification criteria for systemic lupus erythematosus (SLE); prompted by the need for criteria that were both highly sensitive and specific. The net result is improved sensitivity and specificity, but the use of positive ANA requirement along with a longer list of weighted criteria ensures its utility in SLE research (including early or latent SLE), but not clinical practice.

We have options that are endless – we have 28 biologics in rheumatology; 19 approved for RA in the last 20 years, but 15 of these are me-too copies or biosimilars. We currently have 2 JAK inhibitors and may have 3 or 4 by year end. But what we really need is the right drug, at the right time, in the right patient – but how will we know.

Current ACR and EULAR guidelines list TNF-inhibitors (TNFi) abatacept, rituximab, and tocilizumab as being equally effective after methotrexate or as second line therapies when treating rheumatoid arthritis.

By downloading this material, I acknowledge that it may be used only for personal use and personal education and that I will accredit RheumNow.com as the source and owner of this material. Commercial use or mass reproduction of this material without permission from RheumNow (info@rheumnow.com) is prohibited.


