Since the onset of the COVID-19 pandemic numerous anti-rheumatic therapies have been proposed as being potentially beneficial. The mechanistic effects of these agents, either presumed antiviral, anti-inflammatory and anti-thrombotic effects, may benefit mitigate the damage seen with COVID-19 infection.
This review will examine the potential benefits and existing evidence for treating suspected or proven COVID-19 infection with antimalarials, inhibitors of interleukin-6 (IL-6) or interleukin-1 (IL-1) Janus kinase (JAK) inhibitors, TNF inhibitors or colchicine. There are many other antirheumatic and immunosuppressive therapies that are in clinical trials that will not be reviewed here including IVIG, rituximab, calcineurin inhibitors (sirolimus, etc.), apremilast, emapalumab (anti-IFN gamma), etc.
All News
The oral Janus kinase (JAK) inhibitor upadacitinib (Rinvoq) given as monotherapy was more effective than methotrexate alone in methotrexate-naive patients with active rheumatoid arthritis (RA) in a multinational phase III trial.
A one year head-to-head (H2H) trial has shown ixekizumab (IXE) to be superior to adalimumab (ADA) in psoriatic arthritis (PsA); for both skin and articular outcomes.
The SPIRIT H2H study was a 52-week trial of 566 biologic DMARD naive, PsA patients, randomized to received either IXE or ADA. The primary end point was at Wk 24, but the newly published data shows week 52 results for ACR50 and Psoriasis Area and Severity Index 100 responses.
Colchicine has been advocated as a potential anti-inflammatory intervention in patients with the coronavirus 2 infection and clinical trials have been developed to assess its effect in early COVID-2 infection. JAMA has published a randomized clinical trial showing that low dose colchicine had less clinical deterioration without significant changes in biomarkers, such as high-sensitivity cardiac troponin and C-reactive protein.
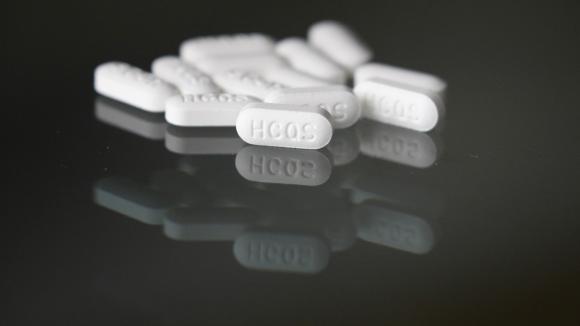
Hydroxychloroquine is one of many medications frequently used in rheumatology practice. Its remarkable versatility is attested by its routine use in lupus, in patients with an autoimmune coagulopathy, in patients with rheumatoid arthritis, as well as in those with a low-level inflammatory arthropathy.