A single-center cohort analysis shows that lung disease is increasingly seen in children with systemic juvenile idiopathic arthritis (SJIA), especially those complicated by macrophage activation syndrome.
Prior to 2013, reports of pulmonary disease in SJIA were rare, but since there have been increasing reports of alveolar hypertension, interstitial lung disease and pulmonary alveolar proteinosis; often with a high mortality rate.
As such, since 2014, the Cincinnati Children’s Hospital Medical Center has seen an increase in lung disease and severe lung disease in SJIA.
All News
Dr. Jack Cush reviews this week's news and journal reports featured on RheumNow.com. PsA v. non-PsA pregnancies, Still's disease, lupus, nutritional supplements and dietary interventions, use of cannabis, tanezumab in OA, CBD oils and more.
First-line treatment of systemic juvenile idiopathic arthritis (JIA) with anakinra (Kineret) was highly effective as monotherapy, minimizing the need for glucocorticoids, a single-center prospective study found.
The drug retention rate of interleukin-1 inhibitors (IL-1) used to treat systemic juvenile idiopathic arthritis (JIA) appears to be quite high according to a new study.
Dr Jack Cush reviews the news from the past week at RheumNow.com.
The NEJM has reported the NIH's Undiagnosed Diseases Network (UDN) study results of genetically identifying new diseases from prospectively followed persons with undiagnosed disorders.
The UDN was formed in 2014 as a network of seven clinical sites, two sequencing cores, a coordinating center, central biorepository, a metabolomics core, and a model organisms screening center. It was established to apply a multidisciplinary model in the evaluation of the most challenging cases and to identify the biologic characteristics of newly discovered diseases.
Some clinical benefits were seen among patients with adult-onset Still's disease treated with tocilizumab (Actemra) in a small clinical trial, but the study's primary endpoint was not met, Japanese researchers reported.
Only inhibitors of IL-1 (canakinumab) and IL-6 (tocilizumab) are FDA approved for use in children with systemic onset juvenile idiopathic arthritis (sJIA). Now, long-term data from the extension studies from two phase III studies shows that canakinumab yields long-term improvements with reduced glucocorticoid dosing with no new safety findings with long-term use.
In July 2018, RheumNow launched a “Live Vote” survey of US and non-US rheumatologists that asked how they diagnose and treat systemic juvenile idiopathic arthritis (sJIA), also known as “Still’s disease”. It appears that many prefer to start therapy with an IL-1 inhibitor, after a course of steroids and MTX/DMARD. Yet, these findings suggest there are significant unmet needs in the diagnosis and management of sJIA patients.
While many autoinflammatory syndromes are driven and managed with select inhibition of IL-1, IL-18 or IL-6, a subset are driven by type I interferon and are referred to as interferonopathies. These monogenic IFN–mediated disorders present in infancy with fevers, systemic inflammation, an IFN response gene signature, inflammatory organ damage, and high mortality.
The New England Journal of Medicine reports that the anti-interleukin (IL)-1β monoclonal antibody canakinumab (Ilaris) was effective in the treatment of three distinct autoinflammatory recurrent fever syndromes (FMF, TRAPS, HIDS) with responses that were far superior to what was see
The identification of a genetic susceptibility locus for systemic juvenile idiopathic arthritis (sJIA) has important implications for treatment of this severe, poorly understood illness, researchers reported.
SOBI has announced that Kineret (anakinra) has been approved by the European Commission (EC) for the treatment of Still’s disease (Systemic Juvenile Idiopathic Arthritis [SJIA] and Adult-Onset Still’s Disease [AOSD]), in all 28 European Union (EU) member states.
Study of 182 hospitalized adult-onset Still's disease patients shows predictive factors for developing macrophage activation syndrome to include: 1. Splenomegaly (OR 5.745), 2. pericarditis (OR 6.5), and 3. ferritin >2000 (OR 4.7). https://t.co/oNsaCL6O92
A study examined whether EGCG suppresses the activation of the NLRP3 inflammasome, thereby effectively preventing gouty #inflammation. It was found that EGCG reduces inflammation in mouse foot tissue making it a promising treatment option for #gout https://t.co/X9O2mbJx6A https://t.co/wgUYz0BmeY
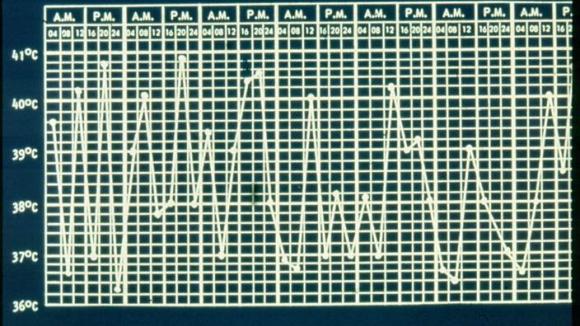
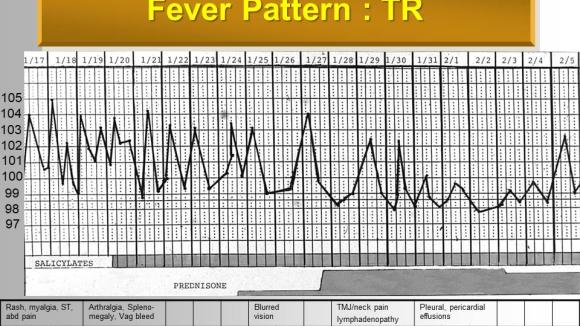
Key features in distinguishing Adult onset Stills disease from Fever of unknown origin: Arthralgia, rash, sore throat, neutrophilia, ferritin >5xULN, LDH based on comparison study of 69 AOSD & 87 FUO pts. 3 or more fever peaks daily makes AOSD less likely. https://t.co/49X4GGludn
QD Clinic - Febrile syndromes; How many days of fever? | from RheumNow - https://t.co/E9TJL3eZaD
Using FMF-KI knockout mice (high TNF levels) researchers find TNF signaling drives pyrin & inflammasome activation; TNF is a critical modulator of pyrin of pyrin-inflammasomopathies like FMF. This is why TNF inhib sometimes work in inflammasomopathies. https://t.co/0EvuTI57tn
Pulmonary arterial hypertension is a very uncommon complication of Adult onset Stills disease - 4.8% of 41 AOSD pts developed PAH - often severe, with a mortality risk. https://t.co/XjyVArMNBl
Vasculitis may complicate autoinflammatory Dz - in FMF (IgA vasculitis, PAN), vasculitis may occur w/ CAPS, TRAPS, HIDS, DIRA, PAPA & Behcets syndromes. Vasculitis is part of DAD2 deficiency (STING-assoc vasculopathy w/ onset in infancy-SAVI (PAN-like) https://t.co/7MKo05pOa3