

Petri SLE Pearls: An Update Save


At the CCR West 2026 conference in Huntington Beach, California, Dr. Michelle Petri updated her Petri Pearls. Some are derived from new data, while others are from her extensive experience caring for patients with systemic lupus erythematosus (SLE). As always, her observations and wisdom have helped clinicians improve patients’ lives through the decades. The valuable pearls she presented are listed here:
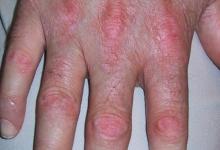
- The “butterfly” rash that some patients report on referral is often not lupus. These rashes are often due to flush/blush, PMLE, rosacea, or seborrheic dermatitis.
- Joint disease in SLE is primarily a capsulitis and/or tenosynovitis, with synovitis sometimes.
- Pleurisy means 2-3 days of 24/7 chest pain with every deep inspiration; otherwise, their chest discomfort is likely from fibromyalgia
- Pericarditis in SLE cannot be treated with rilonacept alone; these patients often need mycophenolate and possibly colchicine. AVOID prednisone as it causes the pericarditis to become harder to treat.
- Distinguish Type 1 (inflammatory) vs Type 2 (noninflammatory) symptoms.
- Fatigue is a big issue in SLE. When societal costs were considered, duloxetine 120 mg/day and pregabalin 450 mg/day were cost-saving relative to amitriptyline based on ICER data. (JAMANetworkOpen.2026;9(2):e2557536.doi:10.1001/jamanetworkopen.2025.57536)
- Start hydroxychloroquine (HCQ) at 400 mg/day and revise the dose based on their whole blood levels. Based on her study, the HCQ dosed by weight does not correlate with HCQ blood levels.
- HCQ improves C3, and low C3 is a risk factor for thrombosis and lupus nephritis (LN). Get an optical coherence tomography (OCT) at baseline and every 5 years. She noted that it would be unusual to have progression of retinopathy once the medicine is stopped. Interestingly, there was study published showing HCQ may help with macular degeneration (Medicina 2023, 59(3), 551; https://doi.org/10.3390/medicina59030551).
- The other benefits of HCQ include reduction in flares, organ damage, lipids, and pregnancy outcomes. It also triples mycophenolate response in LN and improves survival in SLE patients.
- Regarding HCQ whole blood levels, this lab measures the past month of exposure to the medication. Have patients skip their dose on the day HCQ levels are drawn. Often, high levels are due to patients taking the HCQ just before the blood drawn that can cause a spike in the level. Goal HCQ level is 750-1200 ng/mL (ideally, 1000 ng/mL).
- HCQ and hyperpigmentation are usually seen in those who are taking anti-coagulations/anti-platelet agents. It typically improves 2-6 months after stopping HCQ.
- Biotin (vitamin B7) can interfere with a lot of lab measurements, including 25 OH vitamin D, ferritin, and thyroid levels. She recommends her patients stop the supplement for 5 days before lab work or not take it at all. She noted biotin does not help with hair loss in SLE; additionally, a study noted it interferes with cancer detection and may increase the risk for cancer (JCO Oncol Pract 22, 730-731(2026) Volume 22, Number 5 DOI: 10.1200/OP-25-00693).
- Measure 25-OH vitamin D levels: the sweet spot is between 30-50 ng/mL, as vitamin D at these levels improves pregnancy outcomes. It also reduces thrombosis risk.
- Patients with SLE who are pregnant should be seen every 6 weeks.
- Flares are seasonal; typically, in the spring when UV exposure is increased. Joint flares coincide with this.
- Treat flares with pulses of glucocorticoids (oral medrol dosepak or intramuscular) rather than increasing their maintenance dose.
- Anti-phospholipid antibody (aPL) levels fluctuate and can be intermittent, but thrombosis risk remains elevated. Usually, patients make aPLs or the lupus anticoagulant (LAC) only 25% of the time.
- ACE inhibitors/Angiotensin II receptor blockers (ARBs) are protective against venous thrombosis; note that low-dose aspirin does not reduce risk for venous thrombosis in RCTs (but had benefit in the metanalysis).
- Cardiovascular events peak in the first 2 years after diagnosis
- ILD in SLE is rare; she waits until patients have symptoms before testing rather than doing routine screening.
- “Even the first month matters” when it comes to prednisone use. Note that prednisone 20 mg/day for more than a month increases the risk of avascular necrosis and also the risk for depression later.
- “Microalbuminuria is bad.” It increases mortality and major adverse cardiovascular events (MACE). Lupus nephritis doubles the risk of mortality.
- Screen for lupus nephritis frequently.
- The 3rd leading cause of death in patients with SLE is infection. Please vaccinate. She noted vaccines do not cause SLE or lupus flares.
At the end of her lecture, she acknowledged a famous philosopher and author as she thanked her patients for the lessons.
"A pearl is a beautiful thing that is produced by an injured life." --Stephan A. Hoeller
Related Content

Join The Discussion
Concise and Precise
Thank u
Disclosures
Disclosures
The author has no conflicts of interest to disclose related to this subject




If you are a health practitioner, you may Login/Register to comment.
Due to the nature of these comment forums, only health practitioners are allowed to comment at this time.