


Rituximab or Azathioprine for EGPA Maintenance? Save

A French study has shown that rituximab is more effective than azathioprine at maintaining remission in patients with eosinophilic granulomatosis with polyangiitis (EGPA) on chronic prednisone.
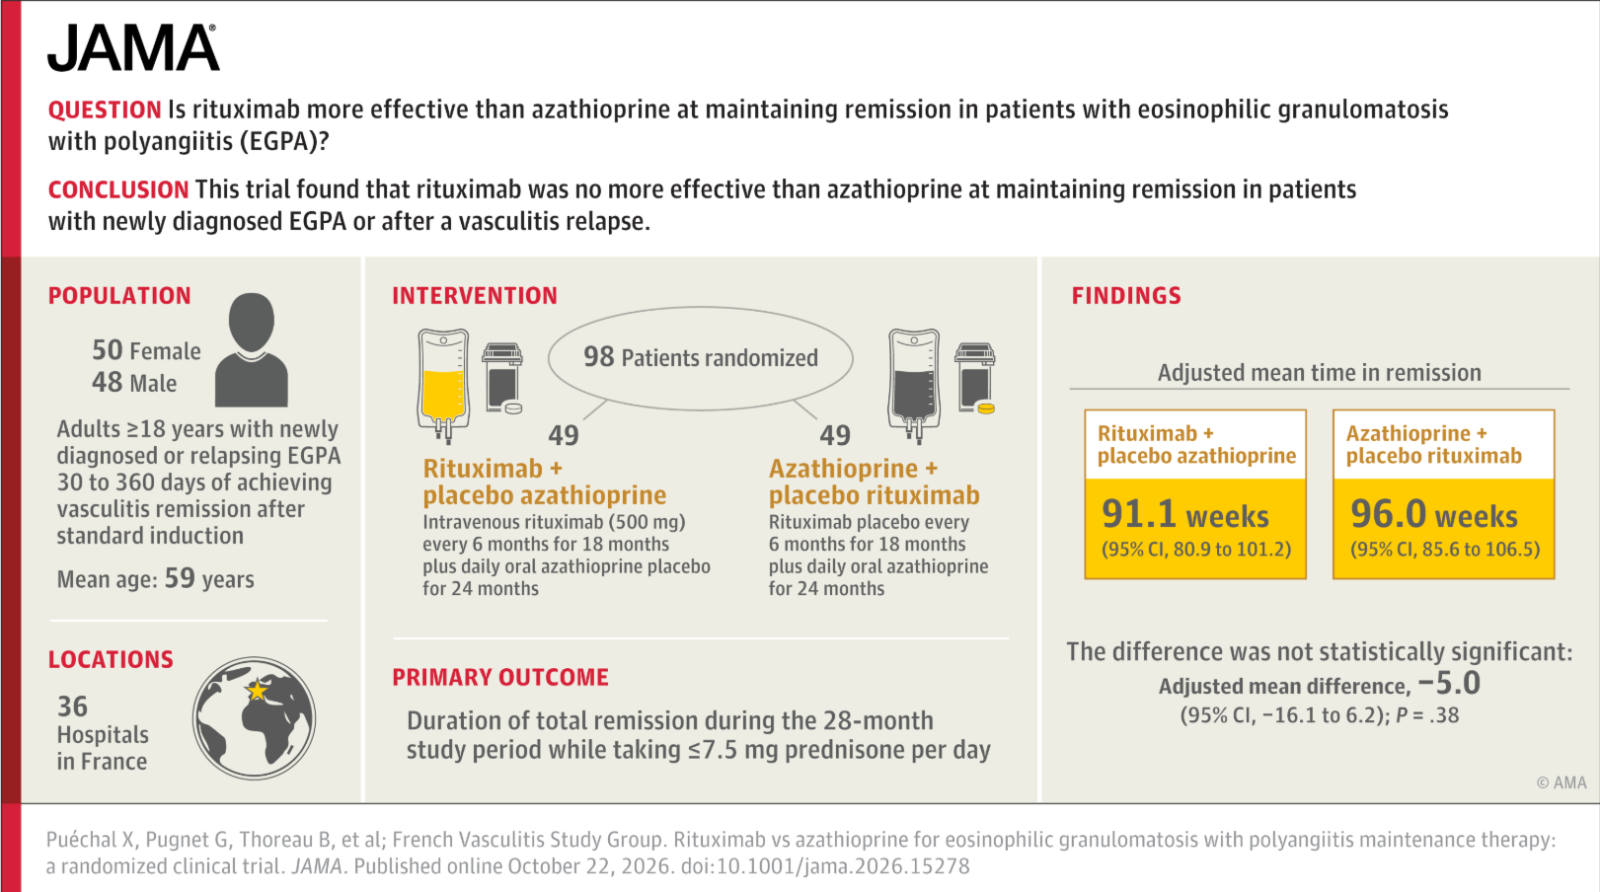
The MAINRITSEG study (MAINtenance of remission with RITuximab vs azathioprine for patients with newly-diagnoSed or relapsing Eosinophilic Granulomatosis with polyangiitis) was a randomized, double-blind, investigator-initiated clinical trial enrolled 98 EGPA patients from 36 hospitals in France. Patients had to have new or or relapsing EGPA and were given a predefined standardized tapering of oral prednisone and either 500 mg of intravenous rituximab every 6 months for 18 months or daily oral azathioprine for 24 months (n = 49). The primary efficacy end point was the duration of total remission during the 28-month study period while taking 7.5 mg/d or less of prednisone. 94% completed the trial.
The mean time in remission was:
- RTX: 91.1 weeks
- AZA: 96.0 weeks (P = .38).
The proportion who remained in remission during the 28-month study 34.7% (RTX) vs 22.4% (AZA); P = .18). Relapse events were 14.3% vs 18.4% (NS).
Rituximab patients had more severe infections (47% vs 24%), primarily due to severe SARS-CoV-2 infections.
Rituximab was no more effective than azathioprine at maintaining remission in patients with newly diagnosed EGPA or after a vasculitis relapse.
In an accompanying editorial, Cartin-Ceba and Wechsler argue that MAINRITSEG’s value lies less in its negative result than in what it disproves: rituximab’s maintenance success in GPA and MPA cannot simply be extrapolated to EGPA. Without an efficacy advantage and roughly double the rate of severe infections, they consider routine use of rituximab over azathioprine difficult to justify in unselected patients.
They note, however, that the trial omitted the most relevant comparator. For patients whose disease is dominated by asthma, sinonasal symptoms, eosinophilia, or glucocorticoid dependence, mepolizumab or benralizumab should generally be preferred. Rituximab is best reserved for selected ANCA-positive, vasculitis-predominant, or high-risk disease. The editorialists conclude that the field should stop seeking one best maintenance drug and move toward phenotype- and biomarker-guided treatment.
Related Content
ADD THE FIRST COMMENT
Disclosures
Disclosures
The author has no conflicts of interest to disclose related to this subject




If you are a health practitioner, you may Login/Register to comment.
Due to the nature of these comment forums, only health practitioners are allowed to comment at this time.